Gut microbiota profiles in Korean children with growth hormone deficiency: a case-control study
Article information

Abstract
Background
The gut microbiota plays an important role in childhood growth and metabolic regulation and may interact with the growth hormone (GH)–insulin-like growth factor-1 axis. However, the gut microbiota characteristics in children with GH deficiency (GHD) are poorly understood.
Purpose
This study aimed to compare the gut microbiota composition and predict the functional profiles of Korean children with GHD and those growing normally.
Methods
In this pilot case-control study, fecal samples were collected from children with biochemically confirmed GHD and age- and sex-matched healthy controls. Gut microbiota composition was analyzed using 16S rRNA gene sequencing. Microbial alpha and beta diversities, taxonomic compositions, and differentially abundant taxa were evaluated. Functional profiles of the gut microbiome were predicted using Phylogenetic Investigation of Communities by Reconstruction of Unobserved States based on the Kyoto Encyclopedia of Genes and Genomes database.
Results
A total of 34 children (11 with GHD, 23 healthy controls) were included in the study. Alpha diversity indices did not differ significantly between groups, whereas beta diversity indices demonstrated a significant intergroup difference (permutational multivariate analysis of variance, P=0.003). At the phylum level, the GHD group showed a higher relative abundance of Proteobacteria and lower abundance of Bacteroidetes. At lower taxonomic levels, taxa including Enterobacteriaceae, Enterobacter, and Citrobacter, which are often associated with dysbiosis, were enriched in the GHD group, whereas beneficial taxa such as Bacteroides and Ruminococcaceae family members were reduced. A functional prediction analysis revealed enrichment of pathways related to adenosine triphosphate-binding cassette transporters, phosphotransferase systems, quorum sensing, and bacterial motility in children with GHD.
Conclusion
Children with GHD showed altered gut microbiota composition and predicted microbial functional pathways despite similar overall microbial diversity. These findings suggest a potential association between gut microbiota alterations and GHD and warrant further investigation in larger well-designed studies.
Key message
Question: Is gut microbiota composition altered in children with growth hormone deficiency (GHD)?
Finding: Children with GHD exhibited altered gut microbiota composition and predicted microbial functional pathways despite similar overall microbial diversity.
Meaning: These preliminary findings suggest a potential association between gut microbiota and pediatric GHD and warrant validation in larger prospective studies.
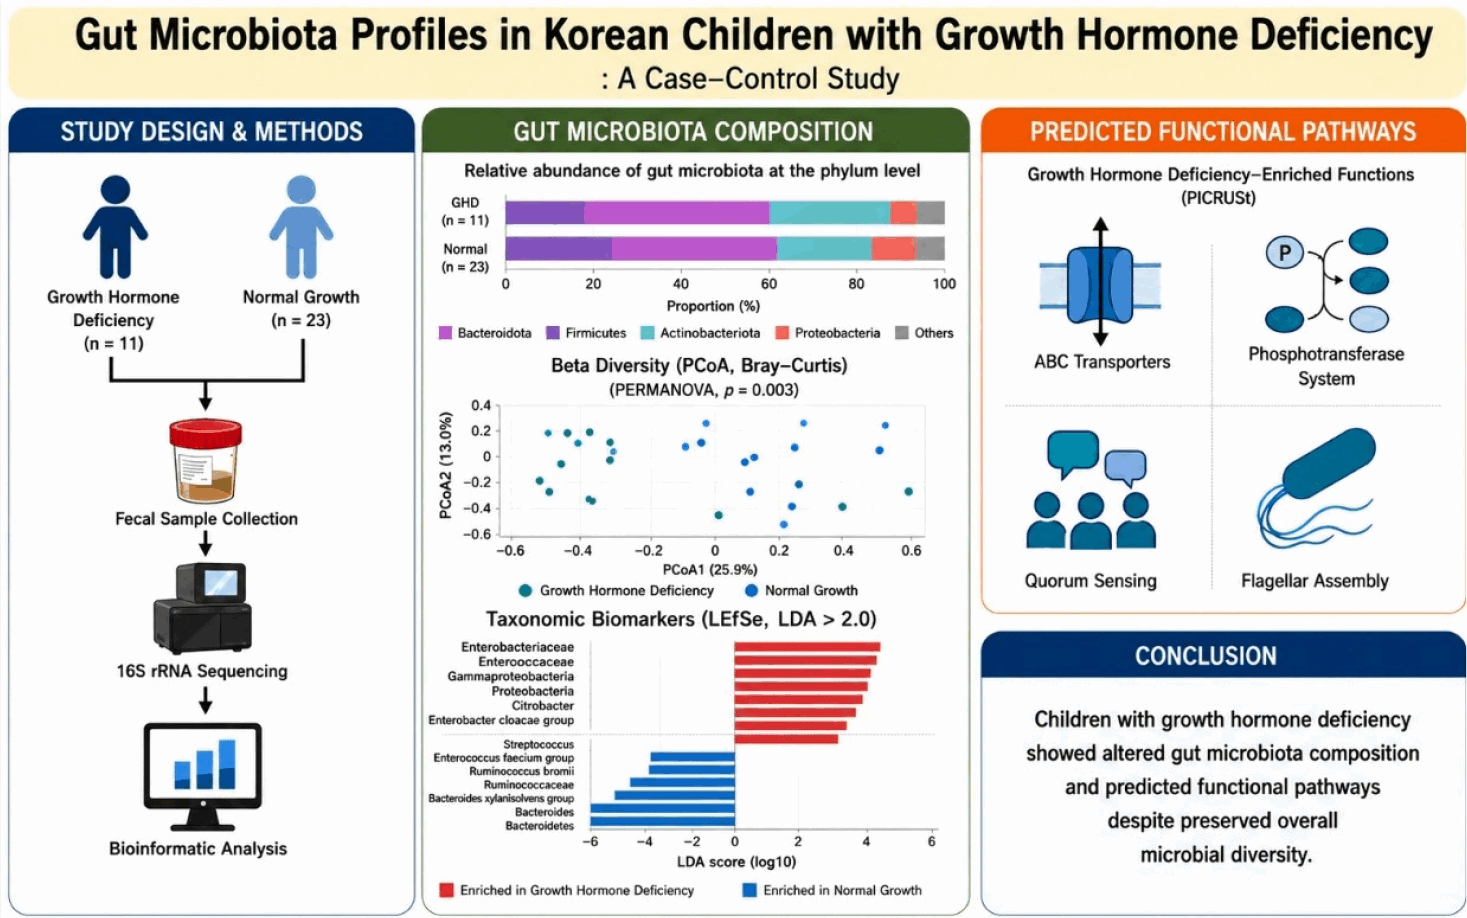
Graphical abstract. GHD, growth hormone deficiency; PCoA, principal coordinates analysis; PERMANOVA, permutational multivariate analysis of variance; LEfSe, linear discriminant analysis effect size; LDA, linear discriminant analysis; ABC, ATP-binding cassette.
Introduction
The human gut ecosystem is home to a densely populated and metabolically active community of microorganisms, collectively known as the gut microbiota [1]. This complex ecosystem plays an important role in nutrient absorption, immune maturation, and metabolic homeostasis [2]. Alterations in gut microbial composition and function have been increasingly implicated in various pediatric disorders, including obesity, allergic diseases, and inflammatory bowel disease [3,4].
Recent studies have also suggested a potential role of the gut microbiota in pediatric conditions associated with impaired growth. Altered microbial diversity and reduced abundance of beneficial taxa have been reported in children with malnutrition, chronic inflammatory diseases, and idiopathic short stature [5,6]. These findings suggest that gut microbial imbalance may contribute to impaired nutrient utilization, low-grade inflammation, and disrupted endocrine signaling involved in normal growth [7,8].
Growth hormone deficiency (GHD) is a significant pediatric endocrine disorder affecting approximately 1 in 4,000 to 10,000 children [9]. It is characterized by inadequate secretion of growth hormone (GH) from the pituitary gland, leading to short stature, delayed bone maturation, and metabolic abnormalities such as increased adiposity and reduced muscle mass [10]. While the hypothalamic-pituitary–GH/insulin-like growth factor-1 (IGF-1) axis is the primary regulator of linear growth, recent evidence suggests bidirectional interactions between the gut microbiota and the endocrine system [11,12].
Experimental studies have demonstrated that gut microbial metabolites, particularly short-chain fatty acids (SCFAs), may influence systemic inflammation, insulin sensitivity, appetite regulation, and IGF-1 production [11,13,14]. Chronic inflammation associated with microbial imbalance may also contribute to GH resistance and impaired growth [15,16].
Despite these biological links, the specific alterations in the gut microbiome associated with GHD remain poorly defined. The gut microbiota is highly dynamic during childhood and is influenced by diet, early-life exposures, and geographic environment [17,18]. Consequently, microbiome signatures identified in one population may not be generalizable to others. In addition, GHD is a heterogeneous disorder with idiopathic, structural, and genetic causes, which may contribute to differences in metabolic and microbial profiles. While a few studies have explored the gut microbiome in children with idiopathic short stature or GHD in other populations, there are currently no published data characterizing the gut microbiome of Korean children with GHD [19,20].
To address this gap, we conducted a pilot case-control study to characterize gut microbiota composition and predicted functional profiles in Korean children with biochemically confirmed GHD compared with healthy children with normal growth.
Methods
1. Study design and participants
This case-control pilot study was conducted at the Department of Pediatrics, Kosin University Gospel Hospital between September 2023 and March 2024. The study protocol was conducted in accordance with the principles of the Declaration of Helsinki and was approved by the institutional review board (IRB) of Kosin University Gospel Hospital (IRB No. 2023-03-034-001). Written informed consent was obtained from the parents or legal guardians of all participants prior to enrollment.
Children diagnosed with GHD and age- and sex-matched healthy controls were enrolled according to predefined criteria. Children were diagnosed with GHD if they met all of the following conditions: (1) height below the 3rd percentile for age and sex; (2) reduced growth velocity (<4 cm/yr); (3) delayed bone age of more than 1 year compared with chronological age; and (4) a peak GH level <10 ng/mL on 2 different GH stimulation tests. GH stimulation tests included clonidine and L-dopa provocation tests. Brain magnetic resonance imaging was performed in all patients with GHD to exclude intracranial structural abnormalities, including pituitary lesions.
Fecal samples in the GHD group were collected after diagnosis and before initiation of recombinant human GH (rhGH) therapy. None of the patients had received rhGH at the time of stool collection.
Healthy control children were recruited from the local community. Inclusion criteria for the control group were height, weight, and body mass index (BMI) between the 25th and 75th percentiles for age and sex, and absence of known growth disorders or chronic illnesses.
Detailed endocrine evaluations, including bone age, pubertal status, GH stimulation test results, and serum IGF-1 levels, were available only for children with GHD and were not collected in the healthy control group.
For both groups, exclusion criteria included a history of chronic gastrointestinal, endocrine (other than GHD), metabolic, oncologic, or psychiatric disorders. To minimize confounding effects on gut microbiota composition, children who had used antibiotics, probiotics, or prebiotics within 2 months prior to fecal sample collection were excluded.
No formal dietary assessment, such as a food frequency questionnaire or 24-hour dietary recall, was performed.
2. Anthropometric measurements
Height and weight were measured using standardized stadiometers and calibrated digital scales with participants wearing light clothing and no shoes. BMI was calculated as weight in kilograms divided by height in meters squared (kg/m²). Height, weight, and BMI were converted to age- and sex-specific standard deviation scores (z scores) based on the 2017 Korean National Growth Charts for children and adolescents.
For children with GHD, bone age delay and reduced growth velocity were additionally confirmed based on medical records obtained at the time of diagnosis.
3. Fecal sample collection and DNA extraction
Fecal samples were collected from all participants using sterile stool collection containers. Samples were immediately frozen at -20°C and transferred to -80°C within 24 hours, where they were stored until further processing.
Total bacterial DNA was extracted from approximately 200 mg of fecal material using the QIAamp DNA Stool Mini Kit (Qiagen, Germany) according to the manufacturer’s instructions. The concentration and purity of extracted DNA were assessed using a NanoDrop spectrophotometer (Thermo Fisher Scientific, USA).
4. 16S rRNA gene sequencing
The V3–V4 hypervariable regions of the bacterial 16S rRNA gene were amplified using the universal primers 341F and 806R. Polymerase chain reaction amplification was performed under standard conditions. Amplicons were purified, and sequencing libraries were prepared according to the Illumina 16S Metagenomic Sequencing Library Preparation protocol.
Paired-end sequencing (2×250 bp) was conducted using the Illumina MiSeq platform (Illumina, USA) at a commercial sequencing facility (CJ Bioscience, Inc., Korea).
5. Bioinformatic and microbiome analysis
Raw sequencing data were processed using the EzBioCloud 16S-based Microbial Taxonomic Profiling pipeline (CJ Bioscience, Inc.) [21]. Low-quality reads, ambiguous bases, and short sequences were filtered, and denoising and chimera removal were performed. Valid reads were clustered into operational taxonomic units at a 97% sequence similarity threshold using the PKSSU4.0 database. After quality filtering, the mean number of valid reads retained per sample was 75,413±33,972 reads. In the GHD group, the mean number of valid reads was 45,325±16,003 per sample (range, 24,569–84,986), whereas in the control group it was 90,051±42,663 per sample (range, 50,214–267,061).
To account for differences in sequencing depth, read counts were rarefied to the minimum sequencing depth across samples prior to diversity analyses.
Alpha diversity was assessed using the abundance-based coverage estimator (ACE), Chao1, Shannon, and Simpson indices. Beta diversity was evaluated using Bray-Curtis dissimilarity and visualized by principal coordinates analysis (PCoA).
PCoA plots were generated based on Bray-Curtis distance matrices, and between-group differences were statistically tested using permutational multivariate analysis of variance (PERMANOVA) with 999 permutations.
Functional profiles of the gut microbiota were predicted using Phylogenetic Investigation of Communities by Reconstruction of Unobserved States (PICRUSt), with predicted gene functions mapped to the Kyoto Encyclopedia of Genes and Genomes orthology database [22].
Differential taxonomic and functional pathway analyses were additionally performed using linear discriminant analysis effect size (LEfSe), which combines nonparametric statistical testing with linear discriminant analysis to identify biologically relevant differences between groups.
6. Statistical analysis
Statistical analyses were performed using IBM SPSS Statistics ver. 22.0 (IBM Co., USA) and the EzBioCloud analytical platform. Continuous variables were expressed as mean±standard deviation or median (interquartile range), as appropriate. Comparisons between groups were conducted using the Mann-Whitney U test for continuous variables and the chi-square test or Fisher exact test for categorical variables.
Differences in microbial alpha diversity and taxonomic relative abundance between groups were assessed using the Wilcoxon rank-sum test. Beta diversity differences were evaluated using PERMANOVA with 999 permutations [23].
Differentially abundant taxa and predicted functional pathways were identified using linear discriminant analysis effect size (LEfSe) [24]. Taxa or pathways with an LDA score >2.0 and a P<0.05 were considered significant.
Results
1. Participant characteristics
A total of 34 children were enrolled in this study, including 11 children diagnosed with GHD and 23 age- and sex-matched children with normal growth. There were no significant differences between the 2 groups with respect to age or sex distribution.
Children in the GHD group exhibited significantly lower anthropometric parameters compared with controls, including height z score (-2.19±0.38 vs. 0.05±0.5, P<0.001), weight z score (-2.01±0.69 vs. -0.02±0.34, P<0.001), and BMI z score (-0.89±0.79 vs. -0.14±0.39, P=0.008) (Table 1).
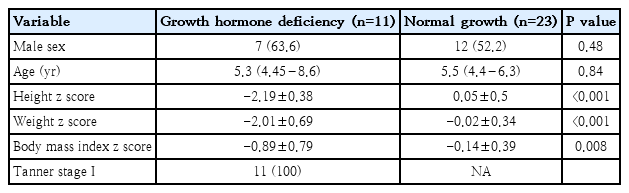
Participants' clinical and anthropometric characteristics
Among children with GHD, the mean peak GH level on stimulation testing was 6.79±2.75 ng/mL. The mean growth velocity before diagnosis was 3.1±0.8 years, and the mean bone age delay was 1.8±0.7 years. The mean serum IGF-1 level in the GHD group was 112.4±38.6 ng/mL.
2. Overall gut microbiota composition
At the phylum level, the gut microbiota of both groups was predominantly composed of Firmicutes, Bacteroidetes, Proteobacteria, and Actinobacteria. However, distinct differences in relative abundance were observed between the 2 groups (Table 2).
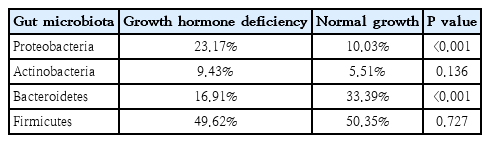
Intergroup comparison of dominant gut microbiota phyla
The relative abundance of Proteobacteria was significantly higher in the GHD group compared with the normal growth group (23.17% vs. 10.03%, P<0.001). In contrast, Bacteroidetes were significantly less abundant in the GHD group (16.91% vs. 33.39%, P<0.001). No significant differences were observed in the relative abundance of Firmicutes or Actinobacteria between the 2 groups.
3. Microbial diversity analysis
1) Alpha diversity
Alpha diversity indices were used to assess within-sample microbial richness and evenness. No significant differences were observed between the GHD and control groups in species richness, as measured by the ACE and Chao1 indices, or in microbial evenness, as measured by the Shannon and Simpson indices (Fig. 1).
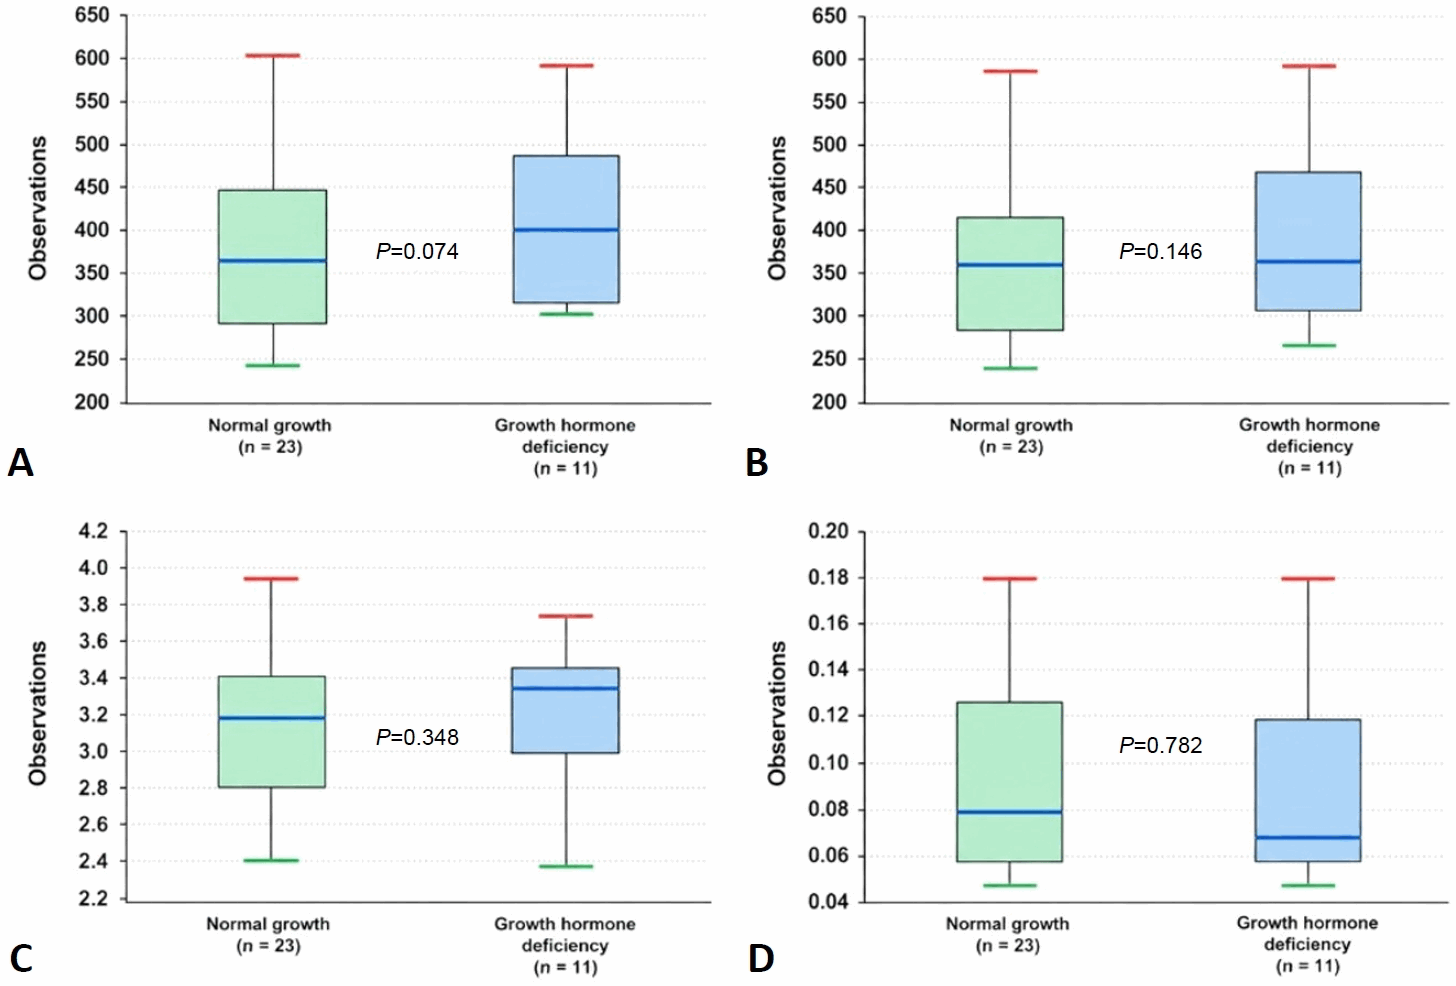
Intergroup comparison of gut microbiome alpha diversity: (A) ACE index, (B) Chao1 index, (C) Shannon index, and (D) Simpson index. Data are presented as median and interquartile range. Statistical comparisons were performed using the Wilcoxon rank-sum test. ACE, abundance-based coverage estimator.
2) Beta diversity
Beta diversity analysis based on Bray-Curtis dissimilarity demonstrated significant differences in microbial community structure between the GHD and normal growth groups (PERMANOVA, P=0.003). PCoA revealed separation of samples according to growth status (Fig. 2), indicating qualitative differences in gut microbiota composition between the 2 groups.
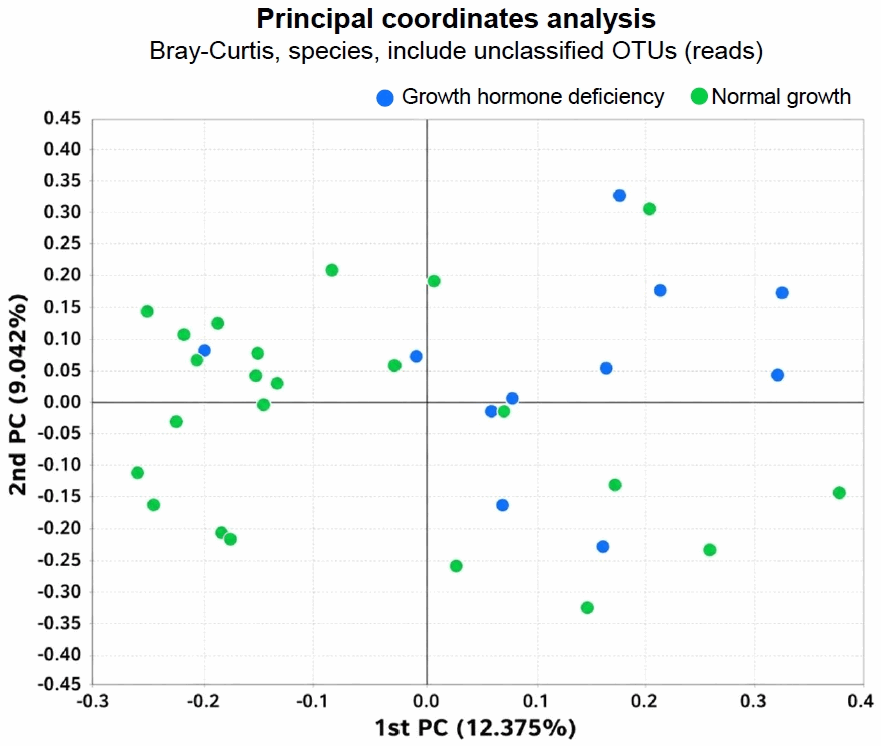
Beta diversity analysis of gut microbiota. Principal coordinates analysis based on Bray-Curtis dissimilarity demonstrating differences in overall gut microbial community structure between children with growth hormone deficiency and normally growing controls. Statistical significance was assessed using permutational multivariate analysis of variance. OTUs, operational taxonomic units; PC, principal coordinate.
4. Taxonomic biomarker identification
Taxonomic biomarkers distinguishing the GHD and normal growth groups were identified using LEfSe with an LDA score threshold > 2.0 (Fig. 3).
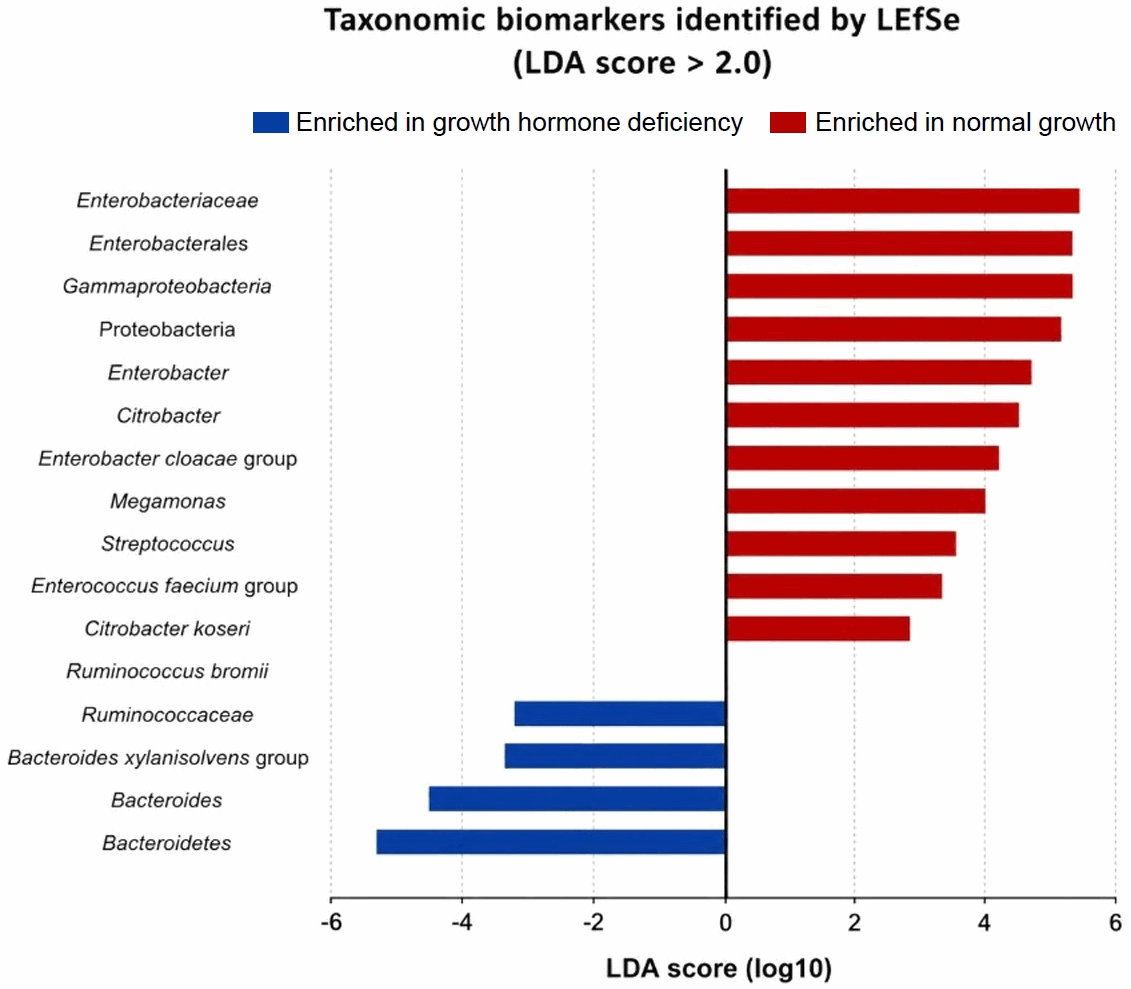
Taxonomic biomarkers associated with growth hormone deficiency identified by LEfSe. Bar plot showing differentially abundant gut microbial taxa of children with growth hormone deficiency versus normally growing controls. Taxa were identified using LEfSe with an LDA score >2.0 and P<0.05. Positive values indicate enrichment in the growth hormone deficiency group, whereas negative values indicate enrichment in the control group. LEfSe, linear discriminant analysis effect size; LDA, linear discriminant analysis.
Multiple taxa belonging to the Proteobacteria lineage were consistently enriched in the GHD group across different taxonomic levels, including Gammaproteobacteria, Enterobacterales, and Enterobacteriaceae. At the genus and species levels, Enterobacter, Citrobacter, Enterobacter cloacae group, Enterococcus faecium group, and Citrobacter koseri were identified as taxa enriched in the GHD group. In addition, taxa belonging to Firmicutes, such as Streptococcus, and Megamonas, were also enriched in the GHD group.
In contrast, the normal growth group was characterized by enrichment of Bacteroidetes-associated taxa, including the genus Bacteroides and the Bacteroides xylanisolvens group. Several members of the Ruminococcaceae family, including Ruminococcus bromii, were also relatively more abundant in children with normal growth.
5. Predicted functional biomarkers of the gut microbiome
Functional profiling of the gut microbiome was predicted using PICRUSt based on 16S rRNA gene sequencing data. LEfSe analysis identified multiple predicted metabolic pathways that were enriched in the GHD group (LDA score >2.0) (Fig. 4).
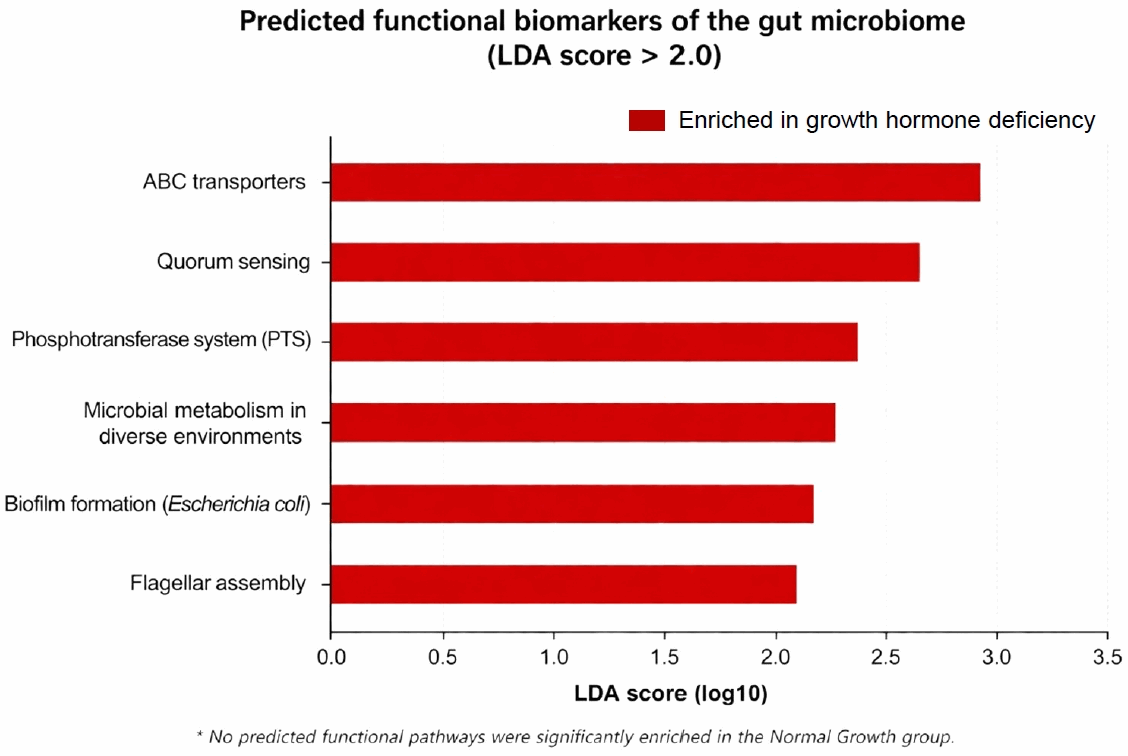
Predicted functional biomarkers of the gut microbiome. LDA effect size results of predicted microbial functional pathways inferred using Phylogenetic Investigation of Communities by Reconstruction of Unobserved States and mapped to the Kyoto Encyclopedia of Genes and Genomes database. Pathways enriched in children with growth hormone deficiency are shown. Only pathways with an LDA score >2.0 and P<0.05 are displayed. LDA, linear discriminant analysis.
These pathways included ATP-binding cassette (ABC) transporters, the phosphotransferase system (PTS), quorum sensing, flagellar assembly, biofilm formation (associated with Escherichia coli), and microbial metabolism in diverse environments. No predicted functional pathways were enriched in the normal growth group at the same threshold.
Discussion
This pilot study is, to our knowledge, the first to characterize the gut microbiota composition and predicted functional profiles of Korean children with biochemically confirmed GHD. Our findings demonstrate that although overall microbial richness and alpha diversity were preserved, children with GHD exhibited differences in gut microbial community structure, characterized by significant alterations in beta diversity, taxonomic composition, and predicted functional pathways. These findings are consistent with the emerging concept of a gut-growth axis and suggest that gut microbial dysbiosis may be associated with pediatric GHD [15,16,25].
A key finding of this study was the increased abundance of Proteobacteria, particularly members of the Enterobacteriaceae family, in children with GHD. In healthy individuals, Proteobacteria typically constitute a minor fraction of the gut microbiota; however, their expansion has been associated with microbial imbalance and inflammatory conditions [26]. Enterobacteriaceae, including genera such as Enterobacter and Citrobacter, which were identified as taxonomic biomarkers in our GHD cohort, are Gram-negative bacteria capable of producing lipopolysaccharide (LPS). Increased LPS exposure has been implicated in low-grade systemic inflammation and metabolic endotoxemia, conditions that may interfere with GH signaling and hepatic IGF-1 production [26-28]. Although inflammatory markers were not directly measured in this study, the observed microbial profile may reflect a gut environment associated with increased inflammatory potential.
We also observed a reduction in Bacteroidetes and members of the Ruminococcaceae family in the GHD group. These taxa are well-known producers of SCFAs, particularly butyrate, which play essential roles in maintaining intestinal barrier integrity, regulating immune responses, and supporting host energy metabolism [29,30]. Reduced abundance of SCFA-producing bacteria may contribute to impaired gut barrier function and altered host metabolic signaling. Thus, the relative depletion of beneficial commensals together with enrichment of potentially pro-inflammatory taxa may represent an unfavorable microbial environment for normal growth.
The relationship between gut microbiota and GHD may also differ according to the underlying etiology of GHD. GHD is a heterogeneous disorder that includes idiopathic, structural, and genetic causes, each of which may involve distinct pathophysiological mechanisms [31]. In particular, genetic forms of GHD related to mutations affecting pituitary development or GH secretion may influence host metabolism, immune regulation, and gut-endocrine interactions in ways that indirectly shape gut microbial composition [31,32]. In turn, gut microbial dysbiosis and low-grade inflammation may further modulate growth-related endocrine signaling through the gut-brain axis [33]. Although the present study did not stratify patients according to GHD etiology because of the limited sample size, future studies incorporating genetic and mechanistic analyses may help clarify whether microbiota alterations differ across specific GHD subtypes.
Interestingly, several Bifidobacterium taxa, including the Bifidobacterium longum and Bifidobacterium breve groups, were enriched in children with GHD despite their generally recognized beneficial role in gut health. This may reflect a compensatory response to microbial imbalance, differences in dietary habits, or altered host-microbe interactions associated with GHD. Increased intake of carbohydrates or caloric supplementation in children with growth concerns may selectively promote the growth of saccharolytic bacteria such as Bifidobacterium. Therefore, the increased abundance of Bifidobacterium in GHD may represent a context-dependent adaptive response rather than a direct indicator of gut health [34,35].
Although alpha diversity indices did not differ significantly between the GHD and control groups, beta diversity analysis demonstrated significant differences in microbial community composition. This pattern, preserved alpha diversity with altered beta diversity, has also been reported in other pediatric conditions associated with impaired growth and metabolic dysregulation [5,36]. These findings suggest that GHD-related microbial alterations may be characterized more by compositional shifts than by a global loss of microbial diversity.
Functional prediction analysis using PICRUSt revealed enrichment of pathways related to ABC transporters, the PTS, quorum sensing, flagellar assembly, and biofilm formation in the GHD group. These pathways are commonly associated with enhanced nutrient acquisition, microbial competitiveness, and environmental adaptability [37-40]. Therefore, the gut microbiota of children with GHD may have altered metabolic potential and microbial interaction patterns. However, because these findings were inferred from 16S rRNA-based prediction rather than direct metagenomic analysis, they should be interpreted cautiously. Further studies are needed to clarify whether these functional alterations influence gut-endocrine communication pathways, including ghrelin-mediated GH secretion [14,41].
Our findings are partially consistent with previous studies examining gut microbiota in growth disorders, which have reported altered beta diversity and differences in specific bacterial taxa. However, results have varied across studies, likely due to differences in ethnicity, dietary patterns, age, pubertal status, and analytical methods. Importantly, this study provides the first microbiome data specific to Korean children with GHD.
Several limitations of this study should be acknowledged. First, the relatively small sample size limits statistical power and generalizability and may have reduced the ability to detect subtle differences in microbial diversity. In addition, formal post hoc power analysis was not performed, and subtle microbiome differences may have remained undetected because of the limited sample size. Second, the cross-sectional design precludes causal inference, and it remains unclear whether gut microbial alterations contribute to the development of GHD or arise as a consequence of hormonal deficiency. In addition, the heterogeneous etiologies of GHD, including possible genetic and structural causes, were not separately analyzed because of the limited sample size. Third, dietary intake was not formally assessed using a food frequency questionnaire or 24-hour dietary recall, despite diet being a major determinant of gut microbiota composition. Fourth, inflammatory markers were not measured, limiting our ability to directly evaluate the relationship between microbial alterations and systemic inflammation. Fifth, detailed endocrine parameters such as bone age, pubertal status, growth velocity, and serum IGF-1 levels were not available in the healthy control group. Finally, predicted functional pathways were inferred using 16S rRNA gene-based analysis rather than direct metagenomic or metabolomic approaches, and therefore should be interpreted cautiously.
In conclusion, Korean children with GHD exhibited altered gut microbiota composition, characterized by enrichment of Proteobacteria-associated taxa, depletion of SCFA-producing commensals, and differences in predicted microbial functional pathways. These findings suggest a potential association between gut microbial alterations and pediatric GHD. Larger longitudinal studies are needed to clarify the mechanistic role of the gut microbiome in growth regulation and to determine whether microbiota-targeted interventions may have therapeutic implications in growth disorders.
Notes
Conflicts of interest
No potential conflict of interest relevant to this article was reported.
Funding
This study received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.
Acknowledgments
The authors sincerely thank the pediatric outpatient nurses and physician assistant nurses at the Department of Pediatrics, Kosin University Gospel Hospital, for their assistance with participant recruitment and fecal sample collection. We also express our deep gratitude to all participating children and their parents or legal guardians for their voluntary participation and cooperation in this study.
Author contribution
Conceptualization: SYC, JHL; Data curation: SYC, SGK, MJ, JHL; Formal analysis: SYC, SGK, GMY, MJ, JHL; Methodology: SYC, SGK, GMY, YRH, MJ, JHL; Project administration: GMY, YRH, JHL; Visualization: YRH; Writing - original draft: SYC; Writing - review & editing: SYC, JHL