





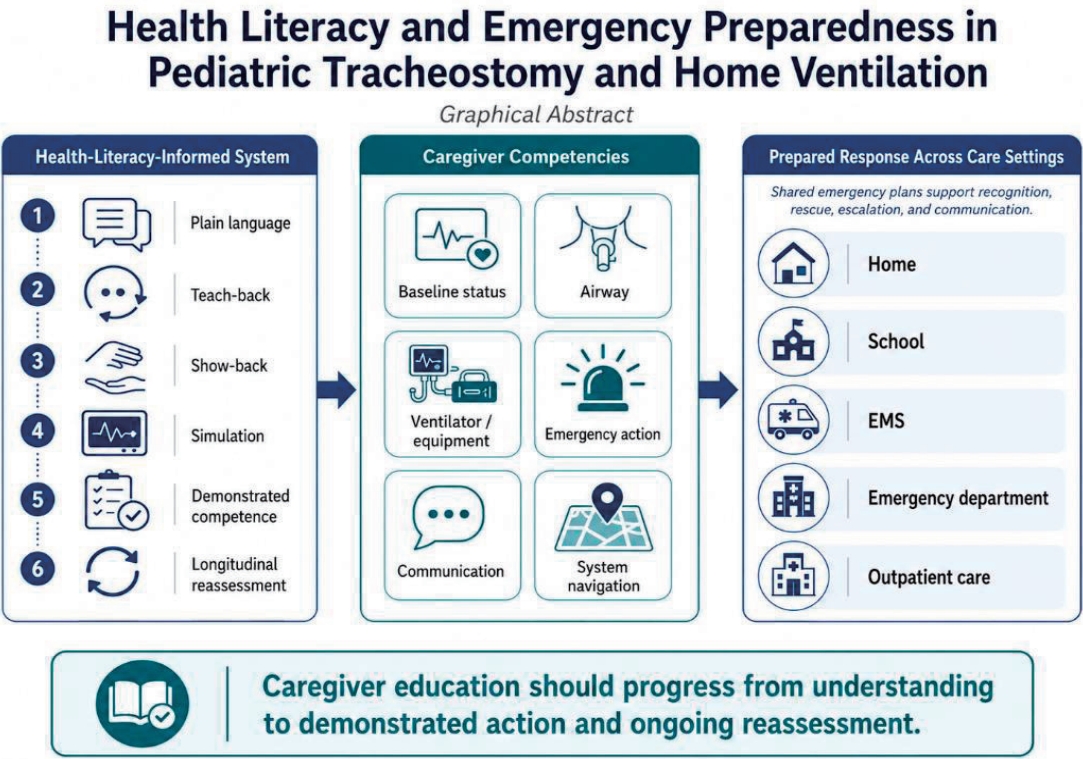
Graphic abstract. EMS, emergency medical services.
Introduction
Health literacy has evolved from a narrow focus on reading ability toward a multidimensional concept involving how people access, understand, appraise, and apply health information. Nutbeam distinguished functional, interactive, and critical health literacy, while later integrative frameworks emphasized the interaction between individual capabilities and the demands imposed by health systems [1-3]. In pediatrics, these capabilities are often exercised by parents and other caregivers. Limited caregiver health literacy has been associated with poorer disease-specific knowledge, medication errors, and greater Emergency Department (ED) use, although these associations do not establish that literacy-focused interventions will improve clinical outcomes [1,4]. A recent mixed-methods pediatric intensive care unit (PICU) study illustrates both the relevance and the difficulty of measuring caregiver health literacy in acute care: only 48 of 329 approached caregivers completed the Newest Vital Sign survey, 79% screened as having adequate health literacy and 21% as having limited health literacy, and providers identified practical barriers related to timing, workflow, and who administered the screen [5]. Because the study was single center, had a low response rate and limited participant diversity, and used a nutrition-label-based instrument that providers felt did not fully reflect the verbal and task-specific demands of critical illness, it should be interpreted as exploratory rather than as a prevalence estimate for all PICU caregivers [5].
Children with tracheostomy and home ventilation place unusually high functional demands on caregivers. Families must combine routine airway care, equipment management, symptom recognition, emergency response, and cross-setting communication, often under time pressure. The American Thoracic Society (ATS) has issued clinical practice guidelines for pediatric tracheostomy care and chronic home invasive ventilation that define important safety structures [6,7]. This review does not attempt to restate those recommendations. Instead, it addresses the implementation gap between receiving guideline-concordant education and being able to perform reliably when the child deteriorates. We use health literacy as the organizing construct that links information, skill, judgment, communication, and system navigation.
This revised narrative synthesis incorporates foundational health-literacy literature, current ATS guidance, caregiver education and simulation studies, recent outpatient and PICU health-literacy research, and literature on Korean home respiratory care. Because the evidence is heterogeneous and is dominated by observational, cross-sectional, qualitative, quality-improvement, and small educational studies, we explicitly distinguish 3 kinds of evidence: direct evidence about caregiver knowledge or performance in pediatric tracheostomy/home ventilation; indirect evidence from broader pediatric health-literacy or educational research; and contextual evidence describing health-system organization and technology-dependent populations. Table 1 summarizes the principal studies and their limitations.
Why children with tracheostomy and home ventilation are a high-risk population
The risk is created by the combination of fragile physiology, dependence on an artificial airway or ventilator, and the transfer of high-stakes tasks from clinical teams to families. Mucus plugging, accidental decannulation, circuit disconnection, battery or power failure, bleeding, infection, and acute respiratory illness may require immediate action before professional help arrives. The burden is also longitudinal: children may cross hospital, home, school, transport, emergency medical services (EMS), and outpatient settings, each with different personnel and opportunities for information loss.
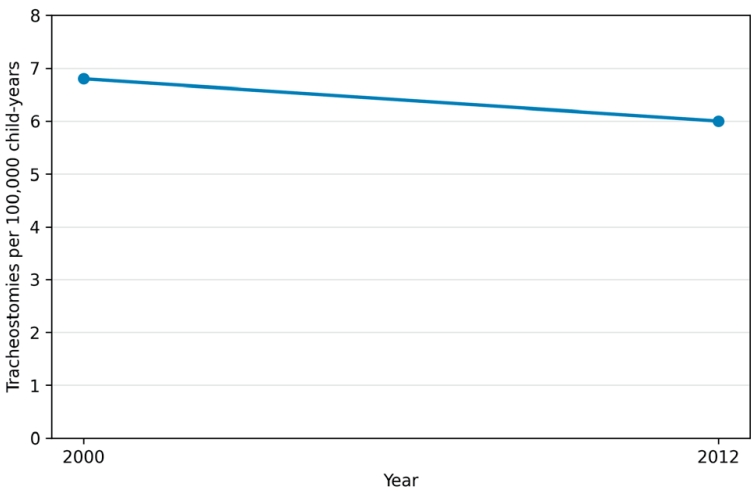
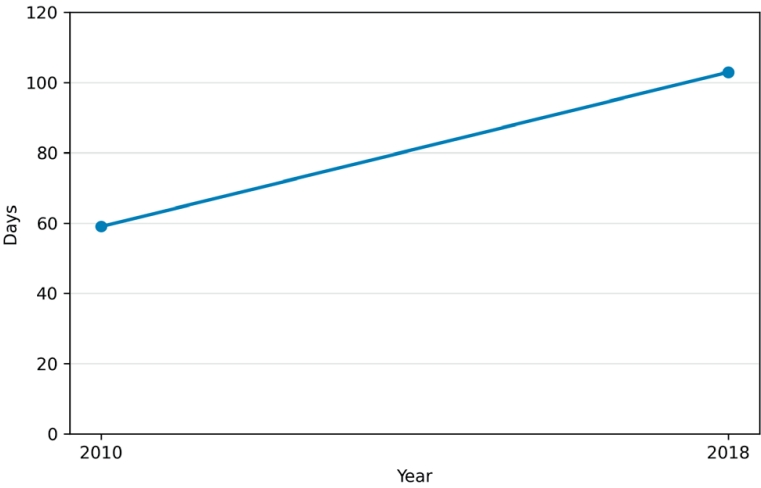
United States (US) population data illustrate an important distinction between procedure incidence and care complexity. From 2000 to 2012, the population-based pediatric tracheostomy rate decreased from 6.8 to 6.0 per 100,000 child-years [8] (Fig. 1). In a separate cohort from 52 US children's hospitals, median total hospital length of stay among children undergoing tracheostomy increased from 59 days in 2010 to 103 days in 2018 [9] (Fig. 2). Because these estimates come from different cohorts, study designs, and time periods, they are presented as separate figures and should not be interpreted as a single continuous trend or as evidence that one pattern caused the other. Together, they show that pediatric tracheostomy is relatively uncommon yet associated with substantial hospital resource use.
Postdischarge events are frequent. In a single-center retrospective cohort of 92 children, 44% had an ED visit with hospital admission within 90 days of discharge; 36% of these encounters were tracheostomy- or respiratory-related [10]. A separate retrospective study of 70 children contributing 163.9 patient-years found 35 severe adverse events, or 0.21 events per patient-year, across home and specialized nursing-facility settings [11]. These studies are limited by retrospective design, setting-specific practices, and inability to isolate caregiver education as a causal factor. Nevertheless, they demonstrate that emergency preparedness is not a theoretical concern.
Caregiver burden and system fragmentation further increase vulnerability. A systematic review of discharge instructions for children with medical complexity included 51 studies; more than half used qualitative or mixed methods, few intervention studies measured objective outcomes, and no randomized trials met inclusion criteria [12]. Barriers included access, coordination, stress, and anxiety, while family-centered and health-literacy-informed strategies were facilitators. The evidence therefore supports attention to the discharge process but is less definitive about which educational intervention changes long-term patient outcomes.
Existing ATS guidance and the implementation gap
The 2016 ATS guideline for pediatric chronic home invasive ventilation recommends standardized discharge criteria, an awake and attentive trained caregiver for children who require continuous support, at least 2 specifically trained family caregivers, ongoing education, pulse oximetry rather than reliance on ventilator alarms alone, equipment maintenance, and essential home equipment [7]. The 2025 ATS tracheostomy guideline similarly recommends a standardized discharge process and comprehensive caregiver training, and strongly recommends continuous presence of an awake and alert trained caregiver for high-risk children [6]. Many of these recommendations are conditional and supported by low or very low certainty evidence, reflecting the ethical and practical difficulty of randomizing core safety practices.
These guidelines answer primarily what structures and safeguards should be present. A health-literacy framework asks a complementary set of questions: What must each caregiver understand and do? How should the team teach and verify those capabilities? How should competence be reassessed after discharge, equipment changes, or real emergency events? Table 2 summarizes the ATS recommendations most directly relevant to caregiver readiness and identifies the additional implementation focus of this review. The proposed domains and educational pathway are therefore intended to operationalize, not replace, guideline recommendations. US key-informant data also show substantial variation in discharge practices, reinforcing the need to make local teaching and competency processes explicit [13].
What caregivers need to learn: 6 core competency domains
The 6 domains are an original, author-derived implementation framework rather than a previously validated taxonomy. We developed them through narrative mapping of 3 sources: multidimensional health-literacy constructs [1-3]; caregiver-readiness and home-safety requirements in the ATS tracheostomy and home invasive ventilation guidelines [6,7]; and recurrent caregiver tasks, emergency scenarios, and assessment targets described in pediatric home mechanical ventilation (HMV)/tracheostomy education literature [14-21]. Overlapping capabilities were grouped by their primary safety function—recognition, airway care, ventilator/equipment management, emergency action, communication, and system navigation— and each domain was retained only if it could be linked to observable caregiver performance. The framework is therefore a practical synthesis intended for implementation and future validation, not a consensus-derived or psychometrically validated instrument. Table 3 aligns each domain with observable performance expectations.
1. Baseline recognition literacy
Caregivers should be able to describe the child's usual respiratory effort, oxygen saturation range, secretion characteristics, ventilator use, oxygen requirement, feeding route, and behavior when well. The safety function of baseline knowledge is change detection: recognizing that the child is different from usual and deciding when that difference warrants action or escalation.
2. Airway literacy
Airway literacy includes tracheostomy purpose, tube size and backup size, suction depth and technique, humidification, stoma care, and signs of obstruction or displacement. The competency is not merely naming supplies; it is linking clinical signs to the next safe action, including suctioning, tube assessment or replacement, oxygenation, manual ventilation, and calling for help.
3. Ventilator and equipment literacy
Caregivers need a practical model of the ventilator circuit, humidification, oxygen delivery, power sources, batteries, and common alarms. Alarm education should begin with the child rather than the machine. The caregiver should assess breathing and perfusion, then evaluate the airway, circuit, connections, and device. Equipment literacy also includes readiness of the emergency bag and rapid access to backup supplies.
4. Emergency-action literacy
Emergency-action literacy is the ability to execute an ordered response to time-sensitive events such as mucus plugging, accidental decannulation, difficult tube reinsertion, sudden desaturation, ventilator disconnection, bleeding, power failure, or cardiopulmonary arrest. Because stress narrows attention and working memory, action pathways should be short, practiced, and anchored to clear escalation thresholds.
5. Communication literacy
During emergencies, caregivers often serve as the most reliable source of child-specific information. They should be able to communicate baseline status, tracheostomy and backup tube size, ventilator settings, usual oxygen needs, recent changes, prior difficult airway events, and the current problem. Written emergency summaries and school or EMS plans reduce reliance on memory alone.
6. System-navigation literacy
Families must know whom to call for respiratory symptoms, equipment malfunction, supply shortages, home nursing problems, medication questions, and urgent deterioration. Navigation failures can become clinical failures when a backup tube is unavailable, power planning is inadequate, or responsibility is unclear across hospital, home-care, equipment, and school systems.
How competencies should be taught and assessed
Education should be treated as performance preparation rather than information transfer. Adult learning theory supports relevance and problem-centered learning; cognitive load theory supports short, sequenced modules; experiential learning supports practice with feedback and reflection; and mastery learning supports progression after predefined performance standards are met [22-25]. These theories are useful design principles, but they should not be mistaken for direct evidence that any single educational method reduces pediatric tracheostomy morbidity. Clinical reviews of pediatric HMV similarly emphasize a broad curriculum spanning disease understanding, recognition of deterioration, airway clearance, ventilator troubleshooting, power planning, emergency response, and follow-up [14]. The contribution of the present framework is to organize those content areas into observable competencies and to link each competency to a method of verification and reassessment.
Stage learning from routine care to emergency response
A practical curriculum can be divided into repeated modules rather than concentrated into a single discharge-period information load. Module 1 establishes the child's baseline, airway anatomy, tube identification, hand hygiene, humidification, and stoma care. Module 2 addresses secretion assessment, suctioning, routine tube change, airway clearance, and bag ventilation. Module 3 covers ventilator function and circuit checks, common alarms, humidification, oxygen delivery, battery and backup-power planning, equipment cleaning, and emergency-bag readiness. Module 4 rehearses mucus plugging, accidental decannulation, difficult reinsertion, sudden desaturation, bleeding, ventilator failure, power failure, and cardiopulmonary arrest. Module 5 integrates communication, EMS activation, written emergency summaries, school and transport planning, follow-up, emergency contact pathways, and supply/equipment support. This content is consistent with the broad educational topics summarized in the pediatric HMV literature while making the expected performance and assessment method explicit [14]. Each module should specify observable learning objectives and the conditions under which the skill must be demonstrated (Table 4).
Use teach-back for understanding and show-back for performance
Teach-back asks the caregiver to explain information in their own words so that the clinician can identify misunderstanding and reteach. Across general healthcare settings, systematic review evidence suggests benefits for knowledge, self-management, and some health outcomes, but implementation and outcome measures are heterogeneous [26]. For tracheostomy and home ventilation, teach-back alone is insufficient for procedural readiness. Showback and direct observation are required for suctioning, tube change, bag ventilation, alarm troubleshooting, and emergency equipment use. The current evidence supports these methods as ways to verify understanding and performance; it does not establish that teach-back by itself reduces emergency visits in this population.
Use simulation selectively and interpret outcomes critically
In a single-center pilot, 24 caregivers completed one simulation-based discharge education session; self-reported comfort and checklist-assessed tracheostomy skills improved, but confidence did not correlate closely with observed skill, and the study did not test long-term clinical outcomes [15]. A later mixed-methods study found positive caregiver experiences that persisted up to 4 years, but among 27 simulation-trained children and 27 matched controls there was no significant difference in tracheostomy-related ED visits within one year (median 2 [interquartile range, 0–2] vs. 1 [interquartile range, 0–2], P=0.2) [16]. Truitt et al. [17] provide a particularly important outpatient perspective: among 52 caregivers, correct responses varied by scenario (88.5% for accidental decannulation, 71.2% for oxygen desaturation, and 65.4% for mucus plugging), only 46.2% answered all 3 scenarios correctly, and 80% reported at least one tracheostomy-related emergency after discharge. Twenty-one percent reported an ED visit or hospitalization for a tracheostomy-related emergency in the preceding year; parents were present during 78.8% of reported outpatient emergencies, compared with home-health nurses during 36.5% [17]. Prior high-fidelity simulation training was not significantly associated with correct responses. However, this cross-sectional questionnaire study did not directly observe performance, used only 3 nonvalidated scenarios, relied on caregiver recall for events, and was not designed to establish a causal effect of simulation [17]. Together, these studies support simulation as a practice and assessment environment, while showing that one-time training, confidence, or prior exposure should not be treated as proof of durable emergency competence.
Assess competence longitudinally
Documentation should distinguish exposure, supervised participation, and independent competence. A statement that education was completed is weaker than a record that a named caregiver independently demonstrated a skill to a defined standard. Reassessment is particularly important after discharge, because real-world problems reveal gaps that are difficult to reproduce in the hospital, and because knowledge and skills may decay. Triggers for reassessment include early postdischarge follow-up, emergency visits or readmissions, changes in tube or ventilator equipment, changes in caregiver support, school entry, and travel.
Critical synthesis of the evidence
The overall evidence is directionally supportive but methodologically limited. The most direct evidence for this review comes from tracheostomy- and HMV-specific studies of caregiver knowledge, observed skills, emergency exposure, and educational interventions [10,11,15-21]. These studies are generally single-center, retrospective, cross-sectional, quality-improvement, or small nonrandomized interventions; they frequently measure knowledge, confidence, or short-term performance rather than mortality, adverse events, or healthcare utilization. The Truitt study is especially informative because it demonstrates persistent outpatient knowledge gaps despite comprehensive training, yet its questionnaire design cannot establish actual emergency performance or the effectiveness of prior simulation [17]. Evidence from broader pediatric health-literacy research, including Reddy et al. [5], helps identify communication and implementation barriers but does not directly measure tracheostomy-emergency competence. Korean epidemiologic and health-system publications define the scale and organization of care but do not test a health-literacy intervention [14,27-29]. Therefore, this review treats standardized education, teach-back, show-back, simulation, and reassessment as reasonable components of a safety system rather than as individually proven strategies for reducing mortality or healthcare utilization. No study identified in this synthesis directly demonstrates that a caregiver health-literacy intervention reduces mortality in children with tracheostomy or home ventilation.
A practical health-literacy-to-safety framework across settings
The framework can be applied as a five-step cycle. First, define the child's baseline and individualized risks, including airway difficulty, secretion burden, ventilator dependence, oxygen needs, feeding and aspiration risks, and prior emergency events. Second, translate those risks into observable caregiver learning objectives across the 6 domains. Third, deliver small, repeated modules using consistent language, demonstration, visual supports, interpreter services when needed, and practice with the equipment used at home. Fourth, verify understanding and performance with teach-back, show-back, direct observation, and simulation for rare high-risk events. Fifth, reassess after discharge and during transitions, using real events and caregiver questions to target reeducation.
The same cycle should extend beyond the primary caregiver. Schools need individualized health plans, trained personnel, emergency equipment, and escalation pathways. EMS and EDs need rapid access to child-specific baseline information, tube size and backup size, ventilator settings, oxygen requirement, and specialist contacts. Home nursing and durable medical equipment teams should use the same core terminology and emergency plan. The goal is a shared emergency language rather than parallel, inconsistent instructions.
Korean context and broader health-system adaptation
Korea provides an important example of why caregiver education cannot simply be imported from a North American model. Park et al. [27] used 2016 National Health Insurance Service (NHIS) data and complementary 2016–2018 data from one tertiary center to describe an early national snapshot after insurance coverage for HMV expanded. Nationwide, 416 children younger than 19 years were prescribed HMV (4.4 per 100,000); 202 (48.6%) had a tracheostomy, and only 95 (22.8%) had claims for home nursing care [27]. In the tertiary-center cohort, 43 of 62 children (69.4%) received invasive ventilation and only 10 (16.1%) received home nursing [27]. These figures support the concern that families often carry a large share of technically complex care, but the study was limited by a single year of national prescription data, reliance on administrative coding and assumed device use, and detailed clinical data from only one tertiary center [27].
The accompanying 2019 editorial by Choi and Park [28] framed the central problem as a care-coordination gap: at that time, community-based primary care and formal medical-home support for ventilator-dependent children were limited, tertiary hospitals remained responsible for both specialized and many routine needs, and families living far from tertiary centers could face repeated long-distance travel and substantial psychological burden. The editorial also described the 2019 launch of a multidisciplinary pediatric home-care pilot involving physicians, nurses, rehabilitation therapists, and nutrition specialists [28]. This article is valuable for health-system interpretation but is an expert commentary rather than an outcomes study, and the system has continued to evolve since publication.
The 2023 narrative review by Kwak [14] places caregiver preparation within the broader clinical risks of pediatric HMV. It summarizes emergency hazards including ventilator failure, secretion-related obstruction, accidental decannulation, bleeding, infection, and acute illness, and cites observational evidence that invasive ventilation was associated with markedly greater odds of unscheduled hospital visits than noninvasive ventilation (odds ratio, 16.3; 95% confidence interval, 2.1–127.4) and that shorter caregiver-education duration was associated with unscheduled admission [14]. The review's educational checklist spans recognition of symptoms requiring urgent attention, airway clearance, ventilator troubleshooting, power supply, self-inflating bag use, cardiopulmonary resuscitation, emergency contacts, and follow-up [14]. These findings are clinically useful for curriculum content, but they are secondary synthesis and should not be interpreted as proof that a particular training duration or educational package causes better outcomes.
The 2026 nationwide NHIS analysis shows how much the population and system burden extend beyond HMV alone [29]. After accounting for overlapping technologies, 3,306 children living at home were identified as technology-dependent; 1,889 required respiratory support, including 459 with tracheostomy and invasive ventilation and 124 with tracheostomy without a ventilator [29]. The prevalence of respiratory technology dependence was similar in Seoul and non-Seoul regions, yet the authors reported that only 4 hospitals provided child-specific home care and 3 were located in Seoul [29]. Across the total technology-dependent cohort, 71.9% had 3 or more complex chronic-condition categories, mean annual inpatient use was approximately 123 days, and 1-year mortality was 17.0% [29]. These data do not measure caregiver health literacy, but they demonstrate the volume of information, coordination, and system-navigation work placed on families and the geographic mismatch between need and specialized home-care capacity. The analysis is limited by claims-based case definitions, a 2018–2019 epidemiologic snapshot, and undercapture of technologies not reliably represented in reimbursed claims [29]. Although the organizational details are Korean, the implementation principle is broader: the 6-domain framework should be adapted to the resources and interfaces of the local health system rather than tied to a particular national model. In systems with more decentralized home nursing or community respiratory support, system-navigation and reassessment responsibilities may be shared with home-care teams; where specialist care is geographically concentrated, telehealth, written emergency plans, EMS coordination, and explicit equipment and supply pathways may assume greater importance. The core competencies are transferable, whereas who teaches them, how often they are reassessed, and which services families must navigate should be locally defined.
Future directions
Future research should move beyond immediate knowledge, satisfaction, and confidence. Priority outcomes include durable observed competence; time to correct action during simulated or real emergencies; emergency calls; ED visits; readmissions; adverse events; caregiver burden; and equity across language, geography, and resource availability. Studies should report the intensity and content of education, who delivered it, how competence was defined, and when skills were reassessed. Multicenter prospective designs and pragmatic implementation studies are needed because single-center educational interventions may be strongly shaped by local staffing and discharge systems.
Digital health and telehealth may extend education after discharge, but current evidence should be interpreted cautiously. In a one-group quasi-experimental study of 37 mothers of children with tracheostomy, a 6-week digital education-supported telehealth intervention improved tracheostomy-care knowledge (P<0.001) but did not significantly change complications (P=0.286) or hospital admissions (P=0.079) [21]. Digital tools should therefore be evaluated as mechanisms for access, reinforcement, remote observation, and targeted reassessment rather than assumed substitutes for hands-on competency assessment. In geographically centralized systems, such as the Korean context described above, telehealth may also help bridge distance, but access, technology skills, language, and the need for direct procedural assessment must be considered.
Implementation science is also needed. Reddy et al. [5] show that even a brief health-literacy screening process can encounter barriers related to timing, caregiver availability, tool relevance, technology access, and whether the administrator is a familiar member of the care team. Their study also raises a broader measurement question: a generic literacy/numeracy screener may not capture the functional, verbal, equipment-specific, and emergency-action capabilities required for tracheostomy and HMV care. Future studies should compare universal health-literacy precautions with targeted screening and should develop or validate task-specific measures of caregiver readiness. Similar implementation questions apply to teach-back, simulation, and reassessment: who is responsible, when does it occur, how is competence documented, and how are failures remediated? A future research agenda should test implementation strategies alongside clinical effectiveness and include long-term assessment of skill retention.
Conclusion
Children with tracheostomy and home ventilation require more than complete discharge instructions. They require caregivers and care partners who can recognize deterioration, maintain the airway, troubleshoot equipment, act during emergencies, communicate child-specific information, and navigate the health system. ATS guidelines define essential safety structures; the author-derived health-literacy framework proposed here addresses how those structures can be translated into observable and reassessed caregiver capabilities. The reviewer-recommended literature strengthens 2 conclusions. First, caregiver knowledge and emergency exposure remain imperfectly aligned with prior training, supporting longitudinal reassessment rather than one-time certification [17]. Second, the organization of postdischarge care shapes what families must be able to do; Korean national data demonstrate substantial technology dependence, high utilization, geographic concentration of child-specific home-care services, and continuing dependence on family coordination [14,27-29]. The evidence base supports structured preparation but remains limited regarding which educational strategies reduce long-term adverse outcomes. A cautious, performance-oriented approach therefore combines guideline-concordant discharge systems with 6 competency domains, staged multimodal teaching, teach-back, show-back, simulation, and longitudinal reassessment across care settings.


 PDF Links
 PubReader
 ePub Link
 XML Download
 PubMed
 Download Citation


