Warning: fopen(/home/virtual/pediatrics/journal/upload/ip_log/ip_log_2026-11.txt) [function.fopen]: failed to open stream: Permission denied in /home/virtual/pediatrics/journal/ip_info/view_data.php on line 93

Warning: fwrite(): supplied argument is not a valid stream resource in /home/virtual/pediatrics/journal/ip_info/view_data.php on line 94
Association between surgical repair timing and mortality in neonates with congenital diaphragmatic hernia: a systematic review and meta-analysis

Volume 69(11); November

< Previous     Next >

Article Contents

Clin Exp Pediatr > Volume 69(11); 2026
Radhakrishna, Balachander, Hansoge Somanath, Aneesh Shenoy, and Balachander: Association between surgical repair timing and mortality in neonates with congenital diaphragmatic hernia: a systematic review and meta-analysis

Abstract

Congenital diaphragmatic hernia (CDH) is a rare congenital anomaly whose management involves a complex interplay between medical and surgical treatments. Stabilization prior to surgery is vital. However, the optimal timing of surgical repair and its relationship with mortality remain unknown. Hence, this meta-analysis aimed to evaluate the association between repair timing and mortality in neonates with CDH. A systematic review and meta-analysis were conducted in accordance with PRISMA (Preferred Reporting Items for Systematic reviews and Meta-analyses) guidelines. The PubMed, NCBI, Cochrane CENTRAL, Google Scholar, CINHAL, Ovid, Scopus, Web of Science, and Epistemonikos databases were searched for articles published through April 2026. Forty studies, including 2 randomized controlled trials, 3 prospective observational studies, and 35 retrospective studies, were included in the meta-analysis. Newborns operated on within 24 hours of life had significantly higher mortality (relative risk [RR], 2.54; 95% confidence interval [CI], 1.76–3.66; P<0.001) than those operated on at or after 24 hours. This association persisted in a subgroup analysis restricted to contemporary studies published since 2000 (RR, 2.57; 95% CI, 1.00–6.62; P<0.001). Additional subgroup analyses demonstrated significantly higher mortality in neonates who underwent repair within 24 hours than in those who underwent repair at 24–48 hours (P<0.001), whereas mortality did not differ significantly between those who underwent repair at 24–48 hours and those who underwent repair after 48 hours (P=0.65). Surgical timing did not significantly alter mortality in a specific subset of newborns requiring ECMO support. In conclusion, a brief period of stabilization of at least 24 hours significantly improved survival among neonates with CDH, whereas delaying surgical repair beyond 48 hours conferred no additional survival benefits.

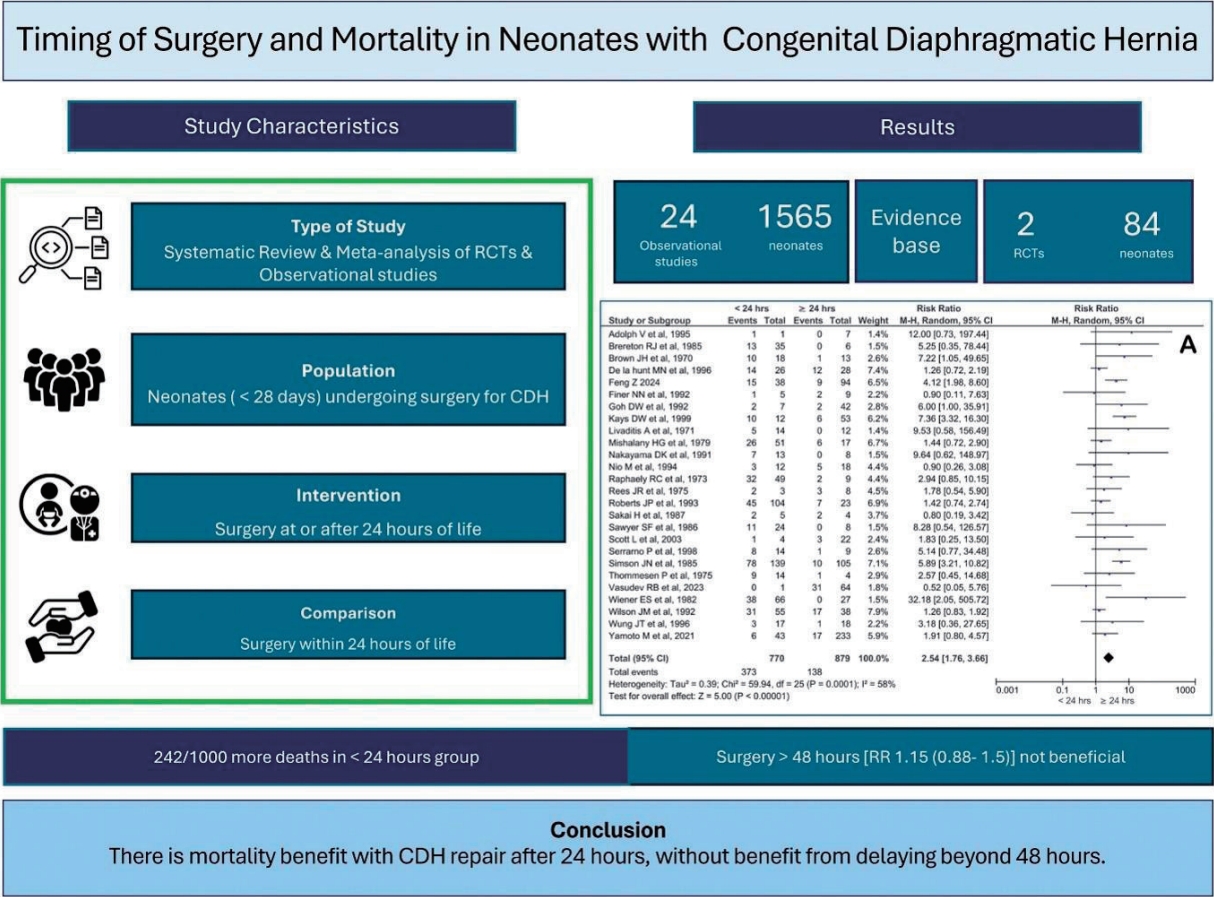
Graphic abstract. RCT, randomized controlled trial; CDH, congenital diaphragmatic hernia; RR, risk ratio

Introduction

Congenital diaphragmatic hernia (CDH) is a rare congenital anomaly with an incidence of 2.3–3.6 cases per 10,000 live births [1-3]. This anomaly allows the abdominal viscera to herniate into the thorax through a diaphragmatic defect that impedes lung development in utero and results in pulmonary hypoplasia. The degree of pulmonary hypoplasia determines the severity of pulmonary hypertension, which contributes to mortality in this condition [4]. The major treatment modalities for this condition include ventilatory support, pulmonary hypertension treatment, and operative repair. The management of CDH has evolved with advances in neonatal and surgical care [5]. Early surgery was historically the standard of care. However, by the 1980s, delayed surgery after a period of stabilization improved the survival rate from 12% to 50% [6,7]. In the last 30 years, protocolized stabilization strategies, along with advances in ventilation, neonatal care, and extracorporeal life support, have improved CDH survival rates to over 80% [8].
Surgical repair is a major step in the treatment of CDH, as it facilitates lung expansion and improves compliance. However, defining the optimal repair timing remains challenging, as criteria for infant readiness for surgery are often subjective and practice varies widely [9]. Repair timing is particularly critical in high-risk infants with severe pulmonary hypertension, as surgery can trigger physiologic instability and deterioration [10,11]. Despite numerous studies to date addressing this issue, including systematic reviews, no meta-analysis has established the optimal surgical timing in children with CDH [12-15]. The updated Canadian consensus also uses level C evidence for surgical readiness; however, it does not mention an optimal surgical timing [8]. The evidence generation for surgical timing would be useful to the clinician to balance mortality due to transitional physiology (pulmonary hypertension) on one hand and the harms of prolonged ventilation, sepsis, and a prolonged hospital stay on the other hand.
Accordingly, this meta-analysis evaluated mortality in neonates with CDH who underwent surgical repair within versus at or after 24 hours. Secondary analyses assessed outcomes using a 48-hour threshold, the association between surgical timing and the need for extracorporeal membrane oxygenation (ECMO), and mortality among neonates requiring ECMO.

Methods

The study evaluated the mortality associated with surgical repair timing in neonates with CDH and was conducted in accordance with Preferred Reporting Items for Systematic reviews and Meta-analyses (PRISMA) guidelines.

1. Eligibility criteria

The study population consisted of neonates (<28 days old) who underwent surgery for CDH. Neonates with eventrations and those who underwent repeat surgeries were excluded. This study included all randomized controlled trials (RCTs), nonrandomized controlled studies, and observational (prospective and retrospective) studies reporting the effects of surgical timing in neonates with CDH. Case series, studies lacking control arms, review articles, editorial comments, and surveys were excluded. Articles that remained inaccessible despite our efforts were excluded.

2. Information sources and search strategy

The study protocol for this meta-analysis was prospectively registered in PROSPERO (CRD42020183555, https://www.crd.york.ac.uk/PROSPERO/view/CRD42020183555). Databases including PubMed, NCBI, Cochrane CENTRAL, Google Scholar, CINAHL, Ovid, Scopus, the Web of Science, and Epistemonikos were searched for articles published through 2023. The search was updated in April 2026. Additional data sources included references to relevant articles and the authors’ personal archives. Keywords included “congenital diaphragmatic hernia/diaphragmatic hernia/Bochdalek hernia” AND “Surg*/therapy/treatment.” No filters were used in the study search. The searches and eligibility determinations were conducted individually by 2 investigators; all differences were resolved by a third investigator. The Rayyan web application was used to screen the articles and foster collaboration.

3. Outcome measures

The primary outcome was postoperative mortality as measured by the relative risks (RRs) or odds ratios (ORs) of neonates undergoing CDH repair within versus at or after 24 hours of life. Additional outcome measures included mortality in neonates who underwent CDH repair within versus at or after 48 hours of life.

4. Subgroup analysis

A subgroup analysis was conducted to evaluate the association between repair timing, the need for ECMO, and mortality among neonates requiring ECMO. To further evaluate the association between surgical timing and mortality, additional subgroup analyses were conducted to compare neonates who underwent surgery within 24 hours of life and those who underwent surgery at 24–48 hours as well as between those who underwent surgery at 24–48 hours and those who underwent surgery after 48 hours. To account for the substantial evolution in neonatal care, ventilation strategies, ECMO availability, and protocolized CDH management, an additional subgroup analysis restricted to studies published since 2000 was performed.

5. Data extraction, analysis, and reporting

All of the data were collected into a pro forma in Microsoft Excel. The characteristics of the included and excluded studies were tabulated. Stratification was performed by study design into RCTs and nonrandomized controlled studies (controlled prospective and retrospective observational studies). A pooled meta-analysis was conducted using Review Manager (RevMan ver. 5.4.1, Cochrane Collaboration, UK). RR was used for dichotomous outcomes, while standardized mean differences were used for continuous outcomes. A forest plot was used to visually depict the data. Absolute mortality reduction was calculated using GRADEpro software (Grading of Recommendations, Assessment, Development and Evaluation Working Group, London, UK) [16]. All pooled effect estimates were reported with 95% confidence intervals (CIs). Associations were assessed using the chi-square test for categorical data and the independent samples t test for continuous data. Statistical significance was set at P<0.05.

6. Heterogeneity, sensitivity, and quality analysis

A heterogeneity assessment was performed and reported using the χ² statistic, I² statistic, and Tau². I² values of 25%–50%, 50%–75%, and ≥75% were considered low, moderate, and high heterogeneity, respectively [17].

7. Risk of bias determination

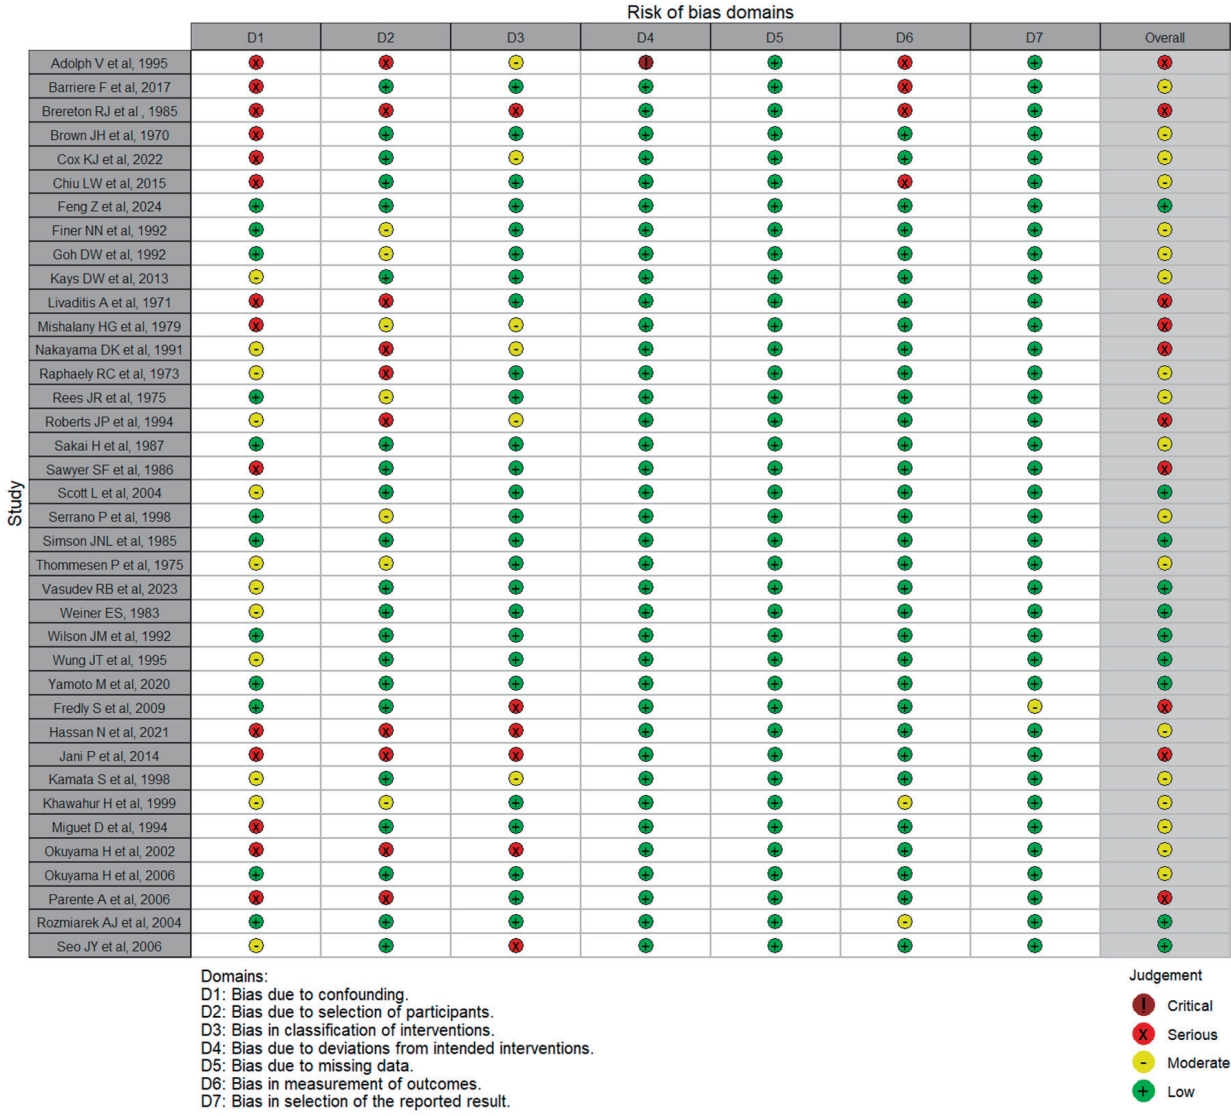
The risk of bias was assessed independently by 2 reviewers using the Risk of Bias 2 tool for RCTs and the Risk Of Bias In Non-randomized Studies of Interventions tool for controlled observational studies. The results are graphically represented using traffic light plots to portray domain-specific judgments. A bubble plot was used to demonstrate the relative contribution of individual studies to the heterogeneity. Funnel plots (using standard errors and log-transformed ORs) were used to assess and graphically represent potential publication bias.

Results

1. Study selection and characteristics

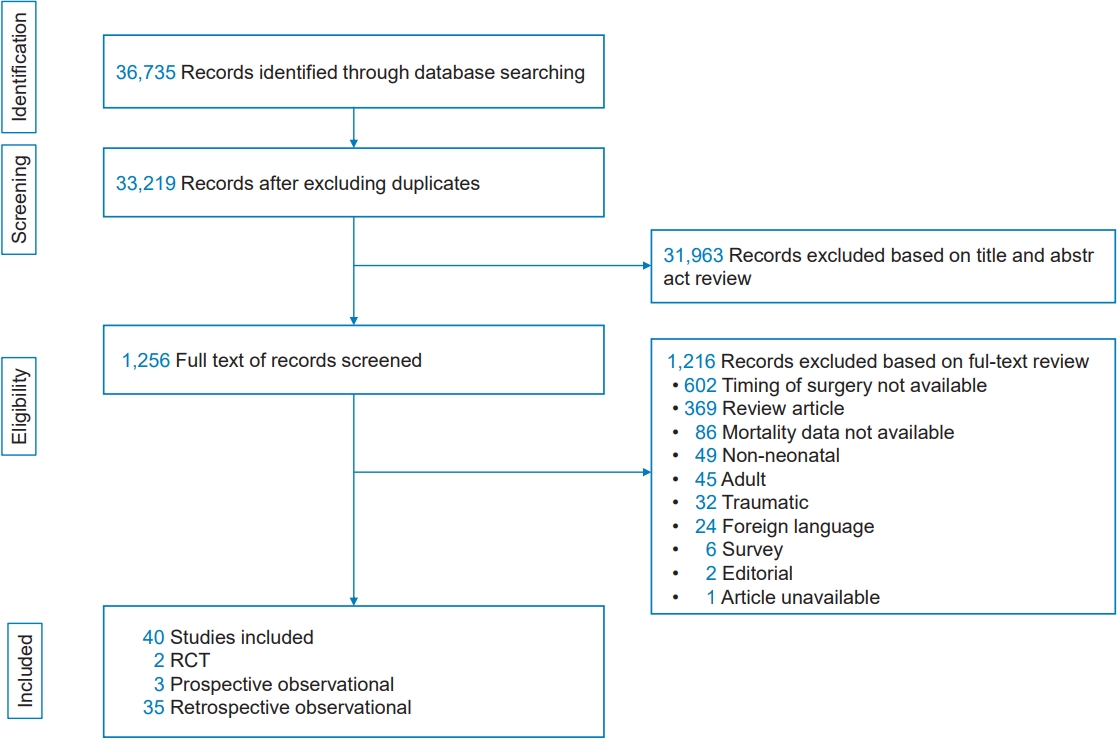
A description of the inclusion process, number of included studies, and reasons for exclusion are shown in Fig. 1 (PRISMA chart). A total of 36,735 articles were identified using the search strategy, and 40 studies comprising 2 RCTs, 3 prospective observational studies, and 35 retrospective studies were included in the meta-analysis (Fig. 1). The study characteristics and patient demographics are summarized in Table 1 and Supplementary Table 1 [16-55]. Criteria for preoperative stabilization varied widely across studies (Supplementary Table 2).

2. Risk of bias assessment

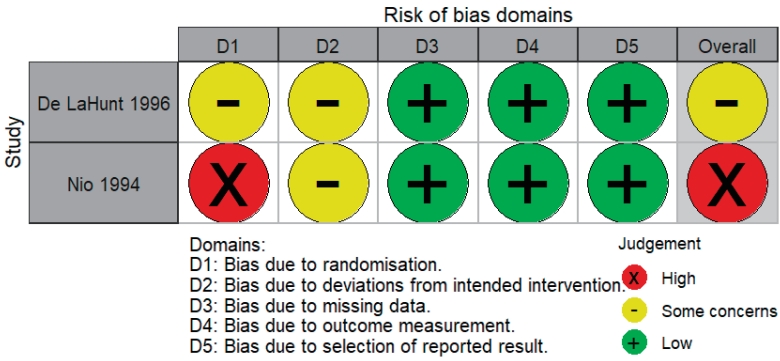
The included RCTs had moderate methodological quality. The study of de la Hunt et al. [35] demonstrated “some concerns” of bias, whereas that of Nio et al. [33] showed “high risk,” primarily due to the randomization and deviations from the intended interventions. The attrition and reporting biases were low in both trials (Fig. 2).
Most nonrandomized studies demonstrated a moderate risk of bias, primarily due to confounding factors. Adjustments for disease severity indicators, such as gestational age, liver herniation, pulmonary hypertension, or use of ECMO, were inconsistently performed. Most studies included consecutive neonates undergoing CDH repair, while some included neonates from different eras; thus, participant selection bias was low to moderate. Bias due to interventional classification was low, as surgical timing was consistently defined across studies. As surgical timing was an objective exposure, the risk of bias from deviations from the intended interventions was low. Biases due to attrition or measurement of the primary outcome were low, as mortality outcomes were clearly defined in most studies (Fig. 3).
The bubble plot illustrated that most studies clustered near the pooled estimates. However, a small number of studies demonstrated larger deviations and contributed disproportionately to the heterogeneity (Supplementary Fig. 1A).
A visual inspection of the funnel plot of the log-transformed ORs against standard errors showed relative symmetry of the studies around the pooled effect estimate. The studies were distributed within the expected 95% CI (Supplementary Fig. 1B and C), indicating no substantial publication bias.

3. Surgery within versus at or after 24 hours of life

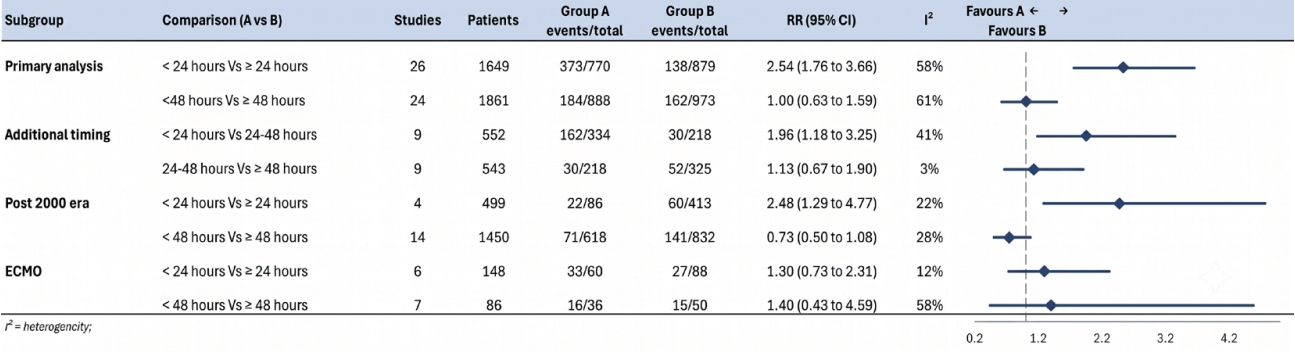
A pooled meta-analysis was performed to assess mortality rates. The analysis included 26 studies (2 RCTs, 1 prospective nonrandomized study, and 23 retrospective studies; Table 1). Newborns operated on within 24 hours of life had an increased mortality rate (373/770 vs. 138/879; P<0.001; RR, 2.54; 95% CI, 1.76–3.66; DerSimonian and Laird [DL] random-effects model) compared to those operated on at or after 24 hours (Fig. 4; Supplementary Fig. 2). These findings were consistent with the Hartung-Knapp-Sidik-Jonkman (HKSJ) random-effects model (RR, 2.55; 95% CI, 1.81–3.61). The 95% prediction interval was 0.67 to 9.75, and the heterogeneity was 58% (Table 2). A GRADE assessment revealed that the newborns operated on within 24 hours were expected to have a 59 per 1,000 higher mortality incidence (RR, 1.16; 95% CI, 0.70–1.94; low certainty) per the pooled analysis of RCTs as well as a 254 per 1,000 higher mortality incidence (RR, 2.75; 95% CI, 2.23–3.38; very low certainty) per the pooled analysis of nonrandomized studies (Supplementary Table 3).

4. Surgery within versus at or after 48 hours of life

The pooled meta-analysis included 24 studies (1 RCT, 3 prospective nonrandomized studies, and 20 retrospective studies; Table 1). Newborns operated on within 48 hours and those operated on at or after 48 hours of life had comparable mortality rates (184/888 vs. 162/973; P=1.000; RR, 1.00; 95% CI, 0.63–1.59; DL random-effects model; Fig. 4; Supplementary Fig. 2). These findings were consistent with HKSJ random-effects model findings (RR, 1.00; 95% CI, 0.60–1.68). The 95% prediction interval was 0.17–5.87, while the heterogeneity was 61% (Table 2).

5. Post-2000 era subgroup analysis

Among the studies published since 2000, neonates who underwent repair within the first 24 hours of life had significantly higher mortality rates than those who were treated at or after 24 hours (22/86 vs. 60/413; P<0.001; RR, 2.48; 95% CI, 1.29–4.77; DL random-effects model; Fig. 4; Supplementary Fig. 3A). The findings were consistent with the HKSJ random-effects model findings (RR, 2.57; 95% CI, 1.00–6.62). The 95% prediction interval was 0.76–8.67, while the heterogeneity was 22% (Table 2).
In contrast, newborns operated on within 48 hours as well as those operated on at or after 48 hours of life had comparable mortality rates (71/618 vs. 141/832; P=0.16; RR, 0.73; 95% CI, 0.50–1.08; DL random-effects model; Fig. 4; Supplementary Fig. 3B), a finding confirmed by the HKSJ random-effects model analysis (RR, 0.73; 95% CI, 0.47–1.15) with a 95% prediction interval of 0.30–1.82 and 28% heterogeneity (Table 2).

6. Additional timing subgroup analyses

Additional subgroup analyses conducted to further characterize the association between repair timing and mortality found that newborns who underwent repair within 24 hours of life had significantly higher mortality rates than those who underwent repair at 24–48 hours of life (162/334 vs. 30/218; P<0.001; RR, 1.96; 95% CI, 1.18–3.25; DL random-effects model; Table 2; Supplementary Fig. 4A). However, mortality did not differ significantly between newborns who underwent repair at 24–48 hours than those who underwent repair after 48 hours of life (30/218 vs. 52/325; P=0.65; RR, 1.13; 95% CI, 0.67–1.90; DL random-effects model; Table 2; Supplementary Fig. 4B).

7. ECMO need and associated mortality

Seven studies including 266 neonates evaluated ECMO utilization; we found no significant difference in need for ECMO (60/115 vs. 88/151, P=0.37; RR, 0.88; 95% CI, 0.66–1.17; DL random-effects model) or mortality rate (33/60 vs. 27/88, P=0.37; RR, 1.30; 95% CI, 0.73–2.31; DL random-effects model) between those neonates with CDH undergoing repair within 24 hours versus at or after 24 hours (Table 2; Supplementary Fig. 5A and B).
Newborns operated on within 48 hours of life had a significantly lower requirement for ECMO (45/247 vs. 67/310; P=0.03; RR, 0.76; 95% CI, 0.59–0.98; DL random-effects model) than those operated on at or after 48 hours of life (Table 2; Supplementary Fig. 5C), but no intergroup difference was noted in ECMO-related mortality (16/36 vs. 15/51; P=0.58; RR, 1.40; 95% CI, 0.43–4.59; DL random-effects model; Table 2; Supplementary Fig. 5D).

Discussion

Despite being a common and life-threatening condition, the optimal timing of surgical repair in newborns with CDH continues to be debated [10,12]. Although multiple studies have evaluated early versus delayed repair, no meta-analysis has definitely established the ideal timing of repair in neonates with CDH [12-15]. To the best of our knowledge, this is one of the first meta-analyses to include all available studies and provide evidence of appropriate surgical timing. In our meta-analysis, the pooled analysis of 26 studies revealed that surgery performed within 24 hours of life was not beneficial; rather, it was associated with a higher risk of mortality. A pooled analysis of 24 studies showed that waiting beyond 48 hours did not confer any additional benefit. The association between repair within 24 hours of life and higher mortality persisted even after restriction of the analysis to studies published since 2000. Additional subgroup analyses demonstrated significantly higher mortality rates among neonates who underwent repair within 24 hours of life than in those who underwent repair at 24–48 hours of life, whereas mortality did not differ significantly between neonates operated on at 24–48 hours of life and those operated after 48 hours of life.
CDH was historically considered a surgical emergency and managed immediately [1,6,7]. Sakai et al. reported a worsening of respiratory compliance after CDH repair in their 1987 research study, which led to a protocolized management approach involving initial cardiopulmonary stabilization before surgical repair [10,12]. Nevertheless, defining the optimal newborn readiness for surgery is often subjective and varies widely. Hence, any delay in surgery can lead to longer hospital stays and chronic pulmonary diseases [9,10,52]. Therefore, identifying the optimal repair timing is essential to reducing morbidity and mortality in newborns with CDH.
To gather more evidence, our meta-analysis included RCTs and non-RCTs. Ultimately, 40 studies were included in the analysis. Most of these studies recommended achieving minimal ventilatory support and no pulmonary hypertension prior to surgical repair [11,28]. In our study, neonates who underwent surgery within 24 hours of life had increased mortality rates. The better survival in neonates who were operated on after 24 hours is probably due to the achievement of adequate physiological stabilization by 24 hours of life as supported by Cox et al., who found that the oxygenation index (OI) and FiO2 requirement significantly decrease in the first 24–48 h of life [55]. Cox et al. [55] also found that an OI ≤9.4 was highly predictive of survival; moreover, 81% of neonates achieved this OI by 24 hours of life, with an additional 12% achieving it by 48 hours of life. A CDH study group (CDHSG) registry including more than 1,000 newborns reported that approximately 62% of surgeries were conducted beyond 24 hours of life [56].
We found no difference in mortality between neonates who underwent surgery within 48 hours and those who underwent surgery at or after 48 hours, likely because most physiological stabilization occurs within 24–48 hours. Cox et al. [55] found no change in mean OI beyond 48 hours of life. Cox et al. [55] also found that delaying surgery after achieving OI ≤9.4 was associated with longer ventilation duration and hospital stay, without a survival advantage. For each day of repair delay, ventilator days increased by 1.4 days and hospital stay increased by 1.5 days [55]. Liu et al. [57] found that delaying surgery beyond 48 h did not affect survival in neonates with CDH.
To account for the substantial evolution in neonatal care, ventilation strategies, ECMO availability, and protocolized CDH management, we performed an additional subgroup analysis restricted to studies published since 2000. The increased mortality in newborns operated on within 24 hours of life was persistently high, even in contemporary-era studies, suggesting that this finding cannot be attributed to historical differences in neonatal care or outdated management practices.
Additional subgroup analyses were conducted to further characterize the relationship between surgical timing and mortality. Neonates operated on within 24 hours of life had significantly higher mortality rates than those operated on at 24–48 hours of life. Moreover, we found no difference in mortality between neonates who underwent surgery at 24–48 hours of life and those who underwent surgery at or after 48 hours of life. Collectively, these results suggest that a short period of physiological stabilization before surgery would be beneficial, whereas delaying surgery beyond 48 hours may not provide additional survival benefits.
A study by the CDHSG registry demonstrated a survival benefit in propensity-matched newborns operated while on ECMO rather than after weaning from it [58]. However, excluding non-repairs, newborns who underwent repair after weaning from ECMO showed higher survival rates [58]. The study also found that neonates who underwent surgery early on ECMO had lower mortality rates than those operated on late on ECMO; however, after the exclusion of non-repairs, no difference was noted in survival between early and late repairs while on ECMO [58]. Studies from the Extracorporeal Life Support Registry demonstrated a survival advantage in newborns who underwent surgery after ECMO decannulation [59,60]. In our meta-analysis, we found no difference in survival based on surgical timing among neonates requiring ECMO.
Our study provides a consolidated assessment of the management of clinically important conditions. It included both RCTs and observational studies, thereby increasing the overall sample size available for evaluating controversial management questions. Moreover, this study was conducted using standard systematic review principles to address practical questions encountered in day-to-day neonatal practice. The additional era-based subgroup analysis restricted to studies published since 2000 improved the contemporary relevance of our findings.
Despite its strengths, this study has certain limitations. As there were few RCTs, our results were mainly derived from pooled analyses of observational studies. Although several studies reported the use of ventilation strategies including high-frequency oscillatory ventilation, inhaled nitric oxide, and other adjunctive therapies, these interventions have not been reported in a standardized manner to permit subgroup analyses. Furthermore, variations in perioperative care, repair indications, ventilation strategies, surgical techniques, ECMO protocols, and institutional management protocols may have introduced clinical heterogeneity and residual confounding factors. Our study also did not adjust for prenatal severity markers, including the observed-to-expected lung–head ratio, liver ratio, liver position, antenatal diagnosis, defect side and size, hernia contents, and pulmonary hypertension, as these parameters were inconsistently reported across the included studies.
In conclusion, newborns operated on at or after 24 hours of life had a lower mortality rate than those operated on within 24 hours of life, including those from contemporary studies. Additional subgroup analyses demonstrated significantly lower mortality in neonates who underwent repair at 24–48 hours than in those who underwent repair within 24 hours of life, whereas mortality rates did not differ significantly between neonates who underwent repair at 24–48 hours versus after 48 hours of life. Our findings suggest the benefit of a brief period of preoperative stabilization and demonstrate that delaying repair beyond 48 hours does not appear to confer an additional survival advantage. Surgical timing did not significantly affect mortality in neonates who required ECMO.
Supplementary materials

Supplementary Table 1.
Demographic variables of included studies for analysis
cep-2026-01837-Supplementary-Table-1.pdf
Supplementary Table 2.
Criteria for stabilization of neonates with CDH for surgery
cep-2026-01837-Supplementary-Table-2.pdf
Supplementary Table 3.
GRADEpro assessment of mortality in newborns operated within 24 hours vs newborns operated at or after 24 hours
cep-2026-01837-Supplementary-Table-3.pdf
Supplementary Fig. 1.
(A) Bubble plot depicting heterogeneity of studies included in the meta-analysis. (B) Funnel plot illustrating no substantial publication bias of studies in newborns with CDH operated on within vs. at or after 24 hours of life. (C) Funnel plot illustrating no substantial publication bias of studies of newborns with CDH operated on within or at or after 48 hours of life. CDH, congenital diaphragmatic hernia; SE, standard error.
cep-2026-01837-Supplementary-Fig-1.pdf
Supplementary Fig. 2.
(A) Forest plot depicting mortality in newborns with CDH operated on within versus at or after 24 hours of life. (B) Forest plot depicting mortality in newborns with CDH operated within 48 hours of life versus those operated at or after 48 hours of life. CDH, congenital diaphragmatic hernia; M-H, Mantel-Haenszel; CI, confidence interval.
cep-2026-01837-Supplementary-Fig-2.pdf
Supplementary Fig. 3.
Post-2000 era subgroup analysis. (A) Forest plot depicting mortality in newborns with CDH operated on within versus at or after 24 hours of life published after 2000. (B) Forest plot depicting mortality in newborns with CDH operated on within vs. at or after 48 hours of life published after 2000. CDH, congenital diaphragmatic hernia; M-H, Mantel-Haenszel; CI, confidence interval.
cep-2026-01837-Supplementary-Fig-3.pdf
Supplementary Fig. 4.
Additional timing subgroup analyses. (A) Forest plot depicting mortality in newborns with CDH operated on within 24 hours versus at 24–48 hours of life. (B) Forest plot depicting mortality in newborns with CDH operated on at 24–48 hours of life vs. at or after 48 hours of life. CDH, congenital diaphragmatic hernia; M-H, Mantel-Haenszel; CI, confidence interval.
cep-2026-01837-Supplementary-Fig-4.pdf
Supplementary Fig. 5.
ECMO use in newborns operated on for CDH. (A) Need for ECMO in newborns with CDH operated on within 24 hours versus at or after 24 hours of life. (B) Mortality in newborns with CDH operated on within 24 hours versus at or after 24 hours of life. (C) Need for ECMO in newborns with CDH operated on within 48 hours versus at or after 48 hours of life. (D) Mortality in newborns with CDH operated on within 48 hours versus at or after 48 hours of life. ECMO, extracorporeal membrane oxygenation; CDH, congenital diaphragmatic hernia; M-H, Mantel-Haenszel; CI, confidence interval.
cep-2026-01837-Supplementary-Fig-5.pdf

Footnotes

Conflicts of interest

No potential conflict of interest relevant to this article was reported.

Funding

This study received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.

Author contribution

Conceptualization: VR, BB, SHS, HAS, SB; Data curation: VR, BB, SHS; Formal analysis: VR, SB; Methodology: VR, BB, SHS, HAS, SB; Project administration: VR, BB, SHS, HAS, SB; Visualization: VR, BB, SHS, HAS, SB; Writing - original draft: VR; Writing - review & editing: VR, BB, SHS, HAS, SB

Fig. 1.
PRISMA (Preferred Reporting Items for Systematic reviews and Meta-analyses) diagram. RCT, randomized controlled trial.
cep-2026-01837f1.jpg
Fig. 2.
Risk of bias - randomized controlled trials.
cep-2026-01837f2.jpg
Fig. 3.
Risk of bias - nonrandomized controlled trials.
cep-2026-01837f3.jpg
Fig. 4.
Summary of pooled analyses evaluating the association between surgical timing and mortality in neonates with congenital diaphragmatic hernia. RR, relative risk; CI, confidence interval; ECMO, extracorporeal membrane oxygenation.
cep-2026-01837f4.jpg
cep-2026-01837f5.jpg
Table 1.
Characteristics of included studies of early versus delayed surgery
No. Study Year Country Duration (yr) Sample size (n) Study design Age at surgery (hr)
Comments
<24 ≥24 <48 ≥48
1 Brown et al. [18] 1970 Australia 20 31 Retrospective 18 13 - -
2 Livaditis et al. [19] 1971 Sweden 18 31 Retrospective 14 12 - - 5 Were operated beyond neonatal period
3 Raphaely et al. [20] 1973 USA 19 58 Retrospective 49 9 - -
4 Rees et al. [21] 1975 USA 6 13 Retrospective 3 8 7 4 2 Were operated beyond neonatal period
5 Thommesen et al. [22] 1975 Denmark 14 29 Retrospective 14 4 - - 11 Were preoperative deaths
6 Mishalany et al. [23] 1979 USA 22 120 Retrospective 51 16 - - Age at surgery not available in 43 neonates, and 10 neonates were not operated
7 Wiener [24] 1982 Unknown Not known 93 Retrospective 66 27 - -
8 Brereton et al. [25] 1985 UK 4 42 Retrospective 35 6 - - 1 Preoperative death
9 Simson and Eckstein [26] 1985 UK 20 253 Retrospective 139 105 172 72 No data available for 9 neonates
10 Sawyer et al. [27] 1986 USA 6 32 Retrospective 24 8 - -
11 Sakai et al. [11] 1987 Canada Not known 9 Retrospective 5 4 8 1
12 Nakayama et al. [28] 1991 USA 3 22 Retrospective 13 8 13 8 1 Preoperative death
13 Finer et al. [29] 1992 Canada 3 16 Retrospective 5 9 10 4 2 Preoperative deaths
14 Goh et al. [30] 1992 UK 4 67 Retrospective 7 42 - - 18 Preoperative deaths
15 Wilson et al. [31] 1992 USA 7 101 Retrospective 55 46 - -
16 Roberts et al. [32] 1993 UK 24 127 Retrospective 104 23 - -
17 Nio et al. [33] 1994 USA 2.5 32 RCT 12 18 12 18 2 From the early group were eliminated as they were not operated
18 Adolph et al. [34] 1995 Canada Not known 10 Retrospective 1 7 1 7
19 de la Hunt et al. [35] 1996 England 6 54 RCT 26 28 - - 28 From group 2 of the study excluded as the timing at surgery was not clear
20 Wung et al. [36] 1995 USA 13 63 Retrospective 17 18 - -
21 Serrano et al. [37] 1998 Puerto Rico 9 32 Retrospective 14 9 - - 9 Preoperative deaths
22 Kays et al. [38] 1999 USA 16 89 Retrospective 12 53 - - 12 Operated from era 1 and 53 operated from era 3 included. Era 2 excluded due to the lack of mortality data, as per the timing of surgery
23 Ontario Congenital Anomalies Study Group [39] 2003 Canada 1 30 Retrospective 4 22 - - 4 Preoperative deaths
24 Yamoto et al. [40] 2021 Japan 6 276 Prospective 43 233 109 167 141 Excluded by the author for various reasons
25 Vasudev et al. [41] 2023 India 8 107 Retrospective 1 64 8 57 Only 65 newborns were operated for CDH
26 Feng et al. [1] 2024 China 11 132 Retrospective 38 94 119 13
27 Miguet et al. [42] 1994 France 4 18 Prospective - - 12 5 1 Preoperative death
28 Kamata et al. [43] 1998 Japan 9 41 Retrospective - - 23 13 5 Preoperative deaths in the delayed group
29 Khawahur et al. [44] 1999 Saudi Arabia 7 33 Retrospective - - 12 9 11 Preoperative deaths
30 Okuyama et al. [45] 2002 Japan 13 30 Retrospective - - 16 11 3 Preoperative deaths
31 Rozmiarek et al. [46] 2004 USA 12 111 Retrospective - - 35 76
32 Parente et al. [47] 2006 Madrid 2 12 Retrospective - - 5 7
33 Seo et al. [48] 2006 South Korea 17 67 Retrospective - - 26 27 14 Preoperative deaths
34 Fredly et al. [49] 2009 Norway 14 27 Retrospective - - 11 9 7 Preoperative deaths
35 Jani et al. [50] 2014 Australia 25 22 Retrospective - - 2 12 8 Preoperative deaths
36 Chiu et al. [51] 2016 USA 9 52 Retrospective - - 12 40
37 Okuyama et al. [52] 2017 Japan 5 441 Retrospective - - 167 242 Missing data on the rest of the neonates
38 Barrière et al. [53] 2017 France 1 89 Prospective - - 56 33 Missing data on the rest of the neonates
39 Hassan and Sarma [54] 2021 India 3 63 Retrospective - - 4 36 23 Preoperative deaths; 5 postneonatal age
40 Cox et al. [55] 2022 USA 19 158 Retrospective - - 48 110

RCT, randomized controlled trial.

Table 2.
Analysis of effect size using DL method and HKSJ method, heterogeneity, and 95% prediction interval
Comparison No. of studies included Metric used Total no. of participants Reported summary ES (95% CI), random-effect model Reanalyzed summary ES (95% CI), DL method
Reanalyzed summary ES (95% CI), HS method random-effect model Heterogeneity 95% Prediction interval
Fixed-effect model Random-effect model Largest study
Timing of surgery, <24 hr vs. ≥24 hr 26 RR 1,649 2.54 (1.76–3.66) 2.76 (2.25–3.37) 2.54 (1.76–3.66) 5.89 (3.21–10.82) 2.55 (1.81–3.61) 58% (0.67–9.75)
Timing of surgery, <48 hr vs. ≥48 hr 24 RR 1,861 1.00 (0.63–1.59) 1.12 (0.90–1.41) 1.00 (0.63–1.59) 0.84 (0.41–1.72) 1.00 (0.60–1.68) 61% (0.17–5.87)
Post-2000 era: surgery, <24 hr vs. ≥24 hr 4 RR 499 2.48 (1.29–4.77) 3.13 (1.69–5.80) 2.48 (1.29–4.77) 1.91 (0.80–4.57) 2.57 (1.00–6.62) 22% (0.76–8.67)
Post-2000 era: surgery, <48 hr vs. ≥48 hr 14 RR 1,450 0.73 (0.50–1.08) 0.69 (0.52–0.91) 0.73 (0.50–1.08) 0.84 (0.41–1.72) 0.73 (0.47–1.15) 28% (0.30–1.82)
Surgery, <24 hr vs. 24-48 hr 9 RR 552 1.96 (1.18–3.25) 2.39 (1.67–3.42) 1.96 (1.18–3.25) 3.09 (1.47–6.46) 1.97 (1.13–3.44) 41% (0.59–6.60)
Surgery, 24-48 hr vs. ≥48 hr 9 RR 543 1.13 (0.67–1.90) 1.07 (0.66–1.74) 1.13 (0.67–1.90) 0.34 (0.08–1.43) 1.12 (0.61–2.03) 3% (0.59–2.12)
Need for ECMO: surgery, <24 hr vs. ≥24 hr 7 RR 266 0.88 (0.66–1.17) 0.81 (0.65–1.01) 0.88 (0.66–1.17) 0.76 (0.57–1.01) 0.88 (0.59–1.31) 31% (0.47–1.62)
Mortality on ECMO: surgery, <24 hr vs. ≥24 hr 6 RR 148 1.30 (0.73–2.31) 1.41 (0.95–2.08) 1.30 (0.73–2.31) 1.19 (0.79–1.80) 1.37 (0.53–3.53) 12% (0.32–5.84)
Need for ECMO: surgery, <48 hr vs. ≥48 hr 8 RR 557 0.76 (0.59–0.98) 0.68 (0.52–0.90) 0.76 (0.59–0.98) 0.85 (0.40–1.82) 0.74 (0.59–0.93) 9% (0.53–1.03)
Mortality on ECMO: surgery, <48 hr vs. ≥48 hr 7 RR 86 1.40 (0.43–4.59) 1.20 (0.67–2.17) 1.40 (0.43–4.59) 0.80 (0.20–3.25) 1.49 (0.26–8.67) 58% (0.05–44.16)

DL, DerSimonian and Laird; HKSJ, Hartung-Knapp-Sidik-Jonkman; ES, effect size; CI, confidence interval; RR, relative risk; ECMO, extracorporeal membrane oxygenation.

References

1. Feng Z, Wei Y, Wang Y, Liu C, Qu D, Li J, et al. Development of a prediction nomogram for 1-month mortality in neonates with congenital diaphragmatic hernia. BMC Surg 2024;24:198.
crossref pmid pmc pdf
2. Paoletti M, Raffler G, Gaffi MS, Antounians L, Lauriti G, Zani A. Prevalence and risk factors for congenital diaphragmatic hernia: a global view. J Pediatr Surg 2020;55:2297-307.
crossref pmid
3. Woodbury JM, Bojanić K, Grizelj R, Cavalcante AN, Donempudi VK, Weingarten TN, et al. Incidence of congenital diaphragmatic hernia in Olmsted County, Minnesota: a population-based study. J Matern Fetal Neonatal Med 2019;32:742-8.
crossref pmid pmc
4. Yang MJ, Russell KW, Yoder BA, Fenton SJ. Congenital diaphragmatic hernia: a narrative review of controversies in neonatal management. Transl Pediatr 2021;10:1432-47.
crossref pmid pmc
5. Morini F, Lally KP, Lally PA, Crisafulli RM, Capolupo I, Bagolan P. Treatment strategies for congenital diaphragmatic hernia: change sometimes comes bearing gifts. Front Pediatr 2017;5:195.
crossref pmid pmc
6. Joshi BS. A case of congenital diaphragmatic hernia. Ind Med Gaz 1940;75:30.

7. Cartlidge PH, Mann NP, Kapila L. Preoperative stabilisation in congenital diaphragmatic hernia. Arch Dis Child 1986;61:1226-8.
crossref pmid pmc
8. Puligandla PS, Skarsgard ED. The Canadian Pediatric Surgery Network Congenital Diaphragmatic Hernia Evidence Review Project: developing national guidelines for care. Paediatr Child Health 2016;21:183-6.
crossref pmid pmc
9. Beres AL, Puligandla PS, Brindle ME; CAPSNet. Stability prior to surgery in congenital diaphragmatic hernia: is it necessary? J Pediatr Surg 2013;48:919-23.
crossref pmid
10. Hollinger LE, Lally PA, Tsao K, Wray CJ, Lally KP; Congenital Diaphragmatic Hernia Study Group. A risk-stratified analysis of delayed congenital diaphragmatic hernia repair: does timing of operation matter? Surgery 2014;156:475-82.
crossref pmid
11. Sakai H, Tamura M, Hosokawa Y, Bryan AC, Barker GA, Bohn DJ. Effect of surgical repair on respiratory mechanics in congenital diaphragmatic hernia. J Pediatr 1987;111:432-8.
crossref pmid
12. Moyer V, Moya F, Tibboel R, Losty P, Nagaya M, Lally KP. Late versus early surgical correction for congenital diaphragmatic hernia in newborn infants. Cochrane Database Syst Rev 2000;2000:CD001695.
crossref pmid pmc
13. Niramis R. Technology assessment for management of congenital diaphragmatic hernia: immediate versus delayed surgery. J Med Assoc Thai 2003;86 Suppl 3:S727-33.
pmid
14. Yunes A, Luco M, Pattillo JC. Early versus late surgical correction in congenital diaphragmatic hernia. Medwave 2017;17:e7081.
crossref pmid
15. Poerwosusanta H, Aditia D, Halim PG, Yuliana M. Optimal early surgery timing for congenital diaphragmatic hernia: a systematic review. Med J Malaysia 2024;79(Suppl 4):77-82.

16. GRADEpro GDT: GRADEpro Guideline Development Tool [Software]. McMaster University and Evidence Prime, 2025 [cited 2026 Jun 20]. Available from: https://methods.cochrane.org/gradeing/gradepro-gdt.

17. Higgins JP, Thompson SG, Deeks JJ, Altman DG. Measuring inconsistency in meta-analyses. BMJ 2003;327:557-60.
crossref pmid pmc
18. Brown JH, Davey RB. Congenital posterolateral diaphragmatic hernia. Aust N Z J Surg 1970;40:30-5.
crossref pmid
19. Livaditis A, Nordstrand A. Congenital posterolateral diaphragmatic hernia in infants. Scand J Thorac Cardiovasc Surg 1971;5:67-73.
crossref pmid
20. Raphaely RC, Downes JJ. Congenital diaphragmatic hernia: prediction of survival. J Pediatr Surg 1973;8:815-23.
crossref pmid
21. Rees JR, Redo SF, Tanner DW. Bochdalek's hernia. a review of twenty-one cases. Am J Surg 1975;129:259-61.
pmid
22. Thommesen P, Hedemand N. Congenital diaphragmatic hernia (Bochdaleck) with special reference to the prognostic influence of congenital cardiac and gastro-intestinal anomalies. Rofo 1975;122:156-60.
crossref pmid
23. Mishalany HG, Nakada K, Woolley MM. Congenital diaphragmatic hernias: eleven years' experience. Arch Surg 1979;114:1118-23.
crossref pmid
24. Wiener ES. Congenital posterolateral diaphragmatic hernia: new dimensions in management. Surgery 1982;92:670-81.
crossref pmid
25. Brereton RJ, Kumar D, Spitz L. Diaphragmatic hernia in neonate. Z Kinderchir 1985;40:75-9.
crossref pmid
26. Simson JN, Eckstein HB. Congenital diaphragmatic hernia: a 20 year experience. Br J Surg 1985;72:733-6.
crossref pmid pdf
27. Sawyer SF, Falterman KW, Goldsmith JP, Arensman RM. Improving survival in the treatment of congenital diaphragmatic hernia. Ann Thorac Surg 1986;41:75-8.
crossref pmid
28. Nakayama DK, Motoyama EK, Tagge EM. Effect of preoperative stabilization on respiratory system compliance and outcome in newborn infants with congenital diaphragmatic hernia. J Pediatr 1991;118:793-9.
crossref pmid
29. Finer NN, Tierney AJ, Hallgren R, Hayashi A, Peliowski A, Etches PC. Neonatal congenital diaphragmatic hernia and extracorporeal membrane oxygenation. CMAJ 1992;146:501-8.
pmid pmc
30. Goh DW, Drake DP, Brereton RJ, Kiely EM, Spitz L. Delayed surgery for congenital diaphragmatic hernia. Br J Surg 1992;79:644-6.
crossref pmid pdf
31. Wilson JM, Lund DP, Lillehei CW, O'Rourke PP, Vacanti JP. Delayed repair and preoperative ECMO does not improve survival in high-risk congenital diaphragmatic hernia. J Pediatr Surg 1992;27:368-72; discussion 373-5.
crossref pmid
32. Roberts JP, Burge DM, Griffiths DM. High-risk congenital diaphragmatic hernia: how long should surgery be delayed? Pediatr Surg Int 1994;9:555-7.
crossref pdf
33. Nio M, Haase G, Kennaugh J, Bui K, Atkinson JB. A prospective randomized trial of delayed versus immediate repair of congenital diaphragmatic hernia. J Pediatr Surg 1994;29:618-21.
crossref pmid
34. Adolph V, Flageole H, Perreault T, Johnston A, Nguyen L, Youssef S, et al. Repair of congenital diaphragmatic hernia after weaning from extracorporeal membrane oxygenation. J Pediatr Surg 1995;30:349-52.
crossref pmid
35. de la Hunt MN, Madden N, Scott JE, Matthews JN, Beck J, Sadler C, et al. Is delayed surgery really better for congenital diaphragmatic hernia?: a prospective randomized clinical trial. J Pediatr Surg 1996;31:1554-6.
crossref pmid
36. Wung JT, Sahni R, Moffitt ST, Lipsitz E, Stolar CJ. Congenital diaphragmatic hernia: survival treated with very delayed surgery, spontaneous respiration, and no chest tube. J Pediatr Surg 1995;30:406-9.
crossref
37. Serrano P, Reyes G, Lugo-Vicente H. Congenital diaphragmatic hernia: mortality determinants in a Hispanic population. P R Health Sci J 1998;17:317-21.
pmid
38. Kays DW, Langham MR, Ledbetter DJ, Talbert JL. Detrimental effects of standard medical therapy in congenital diaphragmatic hernia. Ann Surg 1999;230:340-8; discussion 348-51.
crossref pmid pmc
39. Ontario Congenital Anomalies Study Group. Apparent truth about congenital diaphragmatic hernia: a population-based database is needed to establish benchmarking for clinical outcomes for CDH. J Pediatr Surg 2004;39:661-5.
crossref pmid
40. Yamoto M, Ohfuji S, Urushihara N, Terui K, Nagata K, Taguchi T, et al. Optimal timing of surgery in infants with prenatally diagnosed isolated left-sided congenital diaphragmatic hernia: a multicenter, cohort study in Japan. Surg Today 2021;51:880-90.
crossref pmid pdf
41. Vasudev RB, Kumar N, Gadgade BD, Radhakrishna V, Basavaraju M, Anand A. Factors contributing to mortality in neonates with congenital diaphragmatic hernia and eventration. Afr J Paediatr Surg 2023;20:85-8.
crossref pmid pmc pdf
42. Miguet D, Claris O, Lapillonne A, Bakr A, Chappuis JP, Salle BL. Preoperative stabilization using high-frequency oscillatory ventilation in the management of congenital diaphragmatic hernia. Crit Care Med 1994;22(9 Suppl): S77-82.
crossref pmid
43. Kamata S, Usui N, Ishikawa S, Okuyama H, Kitayama Y, Sawai T, et al. Prolonged preoperative stabilization using high-frequency oscillatory ventilation does not improve the outcome in neonates with congenital diaphragmatic hernia. Pediatr Surg Int 1998;13:542-6.
crossref pmid pdf
44. Khawahur H, Kattan A, Al-Alaiyan S, Saidy K. Congenital diaphragmatic hernia: a local experience. Ann Saudi Med 1999;19:501-4.
crossref pmid
45. Okuyama H, Kubota A, Oue T, Kuroda S, Ikegami R, Kamiyama M, et al. Inhaled nitric oxide with early surgery improves the outcome of antenatally diagnosed congenital diaphragmatic hernia. J Pediatr Surg 2002;37:1188-90.
crossref pmid
46. Rozmiarek AJ, Qureshi FG, Cassidy L, Ford HR, Hackam DJ. Factors influencing survival in newborns with congenital diaphragmatic hernia: the relative role of timing of surgery. J Pediatr Surg 2004;39:821-4; discussion 821-4.
crossref pmid
47. Parente A, Cañizo A, Laín A, Sánchez O, Cerdá J, Molina E, et al. [Are there some clinical factors that indicate the best moment of the surgery in the congenital diaphragmatic hernia?]. Cir Pediatr 2006;19:232-5; Spanish.
pmid
48. Seo JY, Nam SH, Kim DY, Kim SC, Kim ARE, Kim KS, et al. Prognosis of Bochdalek hernia in neonate after change in management principle. J Korean Assoc Pediatr Surg 2006;12:192.
crossref pdf
49. Fredly S, Aksnes G, Viddal KO, Lindemann R, Fugelseth D. The outcome in newborns with congenital diaphragmatic hernia in a Norwegian region. Acta Paediatr 2009;98:107-11.
crossref pmid
50. Jani P, Bidarkar SS, Walker K, Halliday R, Badawi N, Cohen RC. Right-sided congenital diaphragmatic hernia: a tertiary centre's experience over 25 years. J Neonatal Perinatal Med 2014;7:39-45.
crossref pmid pdf
51. Chiu LW, Desai J, Shanti C, Rane S, Agarwal P, Thomas RL, et al. SNAPPE II Score as a predictor of survival in neonates with congenital diaphragmatic hernia: a single center experience. Eur J Pediatr Surg 2016;26:316-21.
crossref pmid
52. Okuyama H, Usui N, Hayakawa M, Taguchi T, Japanese CDH study group. Appropriate timing of surgery for neonates with congenital diaphragmatic hernia: early or delayed repair? Pediatr Surg Int 2017;33:133-8.
crossref pmid pdf
53. Barrière F, Michel F, Loundou AD, Fouquet V, Kermorvant E, Blanc S, et al. One-year outcome for congenital diaphragmatic hernia: results from the French National Register. J Pediatr 2018;193:204-10.
crossref pmid
54. Hassan N, Sarma VP. The outcome of operated neonates with an isolated congenital diaphragmatic hernia in a limited resource scenario: a critical analysis. J Indian Assoc Pediatr Surg 2021;26:32-7.
pmid pmc
55. Cox KJ, Yang MJ, Fenton SJ, Russell KW, Yost CC, Yoder BA. Operative repair in congenital diaphragmatic hernia: how long do we really need to wait? J Pediatr Surg 2022;57:17-23.
crossref pmid
56. Clark RH, Hardin WD, Hirschl RB, Jaksic T, Lally KP, Langham MR, et al. Current surgical management of congenital diaphragmatic hernia: a report from the Congenital Diaphragmatic Hernia Study Group. J Pediatr Surg 1998;33:1004-9.
crossref pmid
57. Liu Q, Hong C, Li X, Jiang H, Tang J. Surgical timing in left mild-to-moderate congenital diaphragmatic hernia. Iran J Pediatr 2021;31:e114111.
crossref pdf
58. Dao DT, Burgos CM, Harting MT, Lally KP, Lally PA, Nguyen HT, et al. Surgical repair of congenital diaphragmatic hernia after extracorporeal membrane oxygenation cannulation: early repair improves survival. Ann Surg 2021;274:186-94.
pmid
59. Delaplain PT, Harting MT, Jancelewicz T, Zhang L, Yu PT, Di Nardo M, et al. Potential survival benefit with repair of congenital diaphragmatic hernia (CDH) after extracorporeal membrane oxygenation (ECMO) in select patients: study by ELSO CDH Interest Group. J Pediatr Surg 2019;54:1132-7.
crossref pmid
60. Robertson JO, Criss CN, Hsieh LB, Matsuko N, Gish JS, Mon RA, et al. Comparison of early versus delayed strategies for repair of congenital diaphragmatic hernia on extracorporeal membrane oxygenation. J Pediatr Surg 2018;53:629-34.
crossref pmid
METRICS Graph View
  • 0 Crossref
  •  0 Scopus
  • 1,048 View
  • 47 Download