





 ,
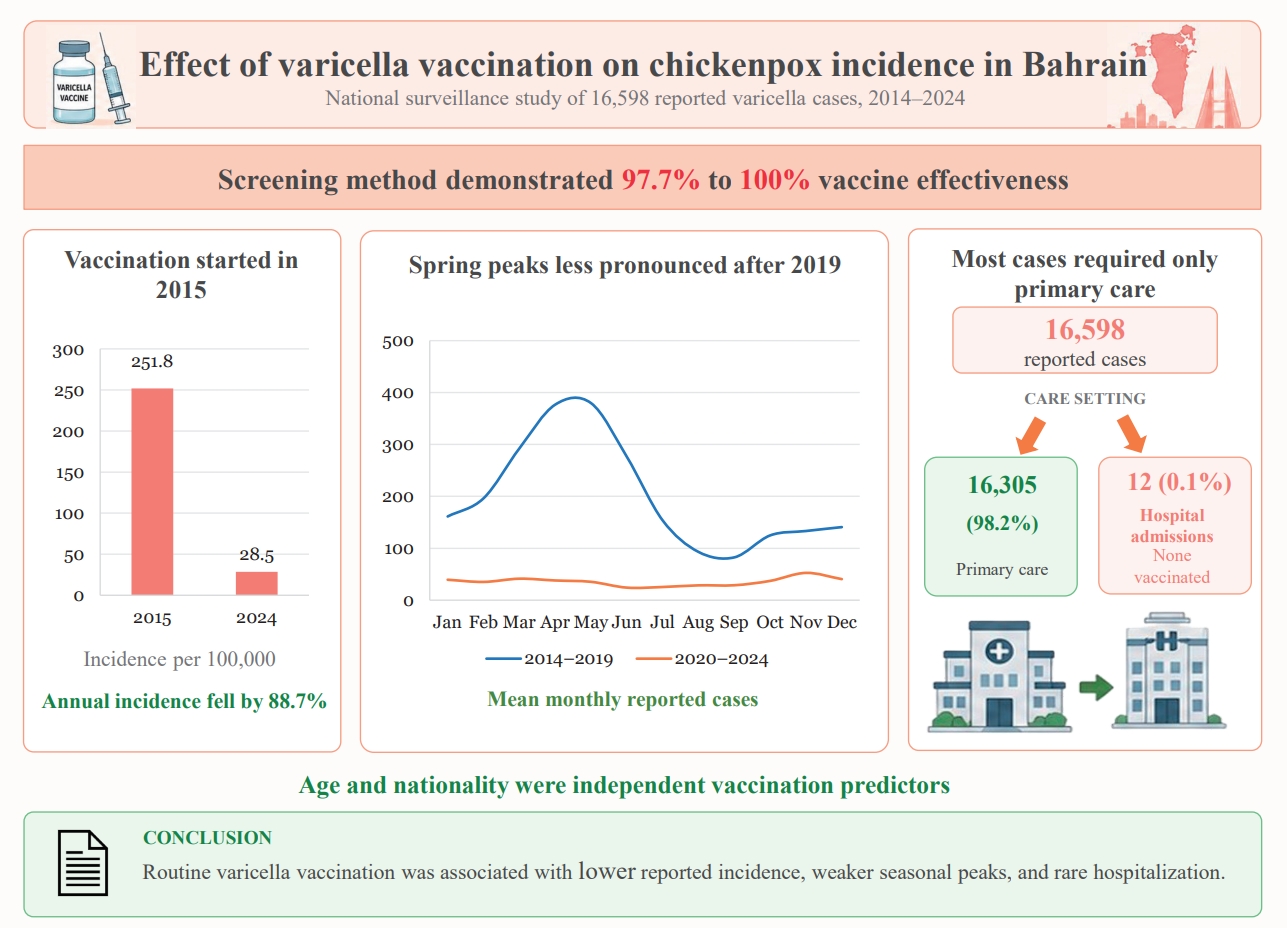
Graphic abstract. Effect of varicella vaccine introduction on chickenpox incidence in Kingdom of Bahrain.
Introduction
Varicella-zoster virus (VZV), a member of the Herpesviridae family, causes primary varicella (chickenpox), typically acquired during childhood [1-3]. Following primary infection, the virus remains latent in the dorsal root ganglia and may later reactivate to herpes zoster [3]. The incubation period ranges from 10 to 21 days (average 14–16 days), and transmission occurs via airborne respiratory droplets or direct contact with vesicular lesions [1,4].
Chickenpox commonly presents with malaise, fever, and a generalized pruritic rash that begins as macules and progresses to vesicles, predominantly affecting the scalp, trunk, and face [2].
Despite the contagious nature of the disease, chickenpox is usually self-limiting in children, and typically resolves within 4–5 days from the infection [5]. However, complications may occur in immunocompromised patients and adult individuals. The complications associated with chickenpox include pneumonia, secondary bacterial infection, encephalitis, cerebral ataxia, and hepatitis [6-8]. VZV remains dormant in multiple sensory ganglia and upon reactivation can lead to several central and peripheral nervous system manifestations such as small vessel vasculitis, shingles and stroke [9,10].
The incidence of VZV infection varies in different countries. In 2019, the cases recorded globally reached about 84 million for both sexes and all ages [11]. The highest incidence is in children aged between 1–6 years old [5]. In Germany, the number of casese of VZV infections rose to 750,000 individuals before the introduction of the vaccine [1]. The surveillance data of VZV infections for the Gulf Cooperation Council (GCC) countries revealed a decrease in the incidence from 304.5 cases per 100,000 in Bahrain in 2013 to 127.1 cases per 100,000 in 2015 [12]. This drop in the incidence was also noted in Saudi Arabia. Between 2007 and 2012, the average monthly incidence of chickenpox cases in Saudi Arabia was 34.9 [13]. The mean incidence rate per 100,000 in Saudi Arabia dropped from 2,580.5±474.1 in 1994–1997, to 767.6±129.8 after the varicella vaccine introduction [14].
The problem of VZV infection lies in the severe complications that may arise as a result of the disease, creating an economic burden on many countries due to increased need for hospitalization and healthcare support [15]. The burden of disease is measured in disability-adjusted life years (DALYs) [16]. The DALY of varicella/herpes zoster has been collected from a study and was about 0.9 million [11]. Over the past 30 years, the global incidence of varicella-zoster infections has risen while the number of age-standardized deaths and DALY has reduced. The age-standardized incidence rate and the age-standardized DALY rate were highest in Western Sub-Saharan Africa and high-income Asia-Pacific [17].
The first varicella vaccine was produced in Japan in the 1970s [11]. The vaccine is live attenuated and can prevent primary infection in children older than 12 months [18]. Clinical trials found the vaccine to be effective, offering 70%–90% protection for 7–10 years [19]. Zhang et al. [11] also showed that the vaccine is safe and effective, leading to a reduction in the risk, severity, and death rates of ≥95%. Vaccinations are essential to reduce the incidence of the disease and help minimize the disease severity due to the high seroconversion rate in children after the administration of the 2 doses of the vaccine [15].
The Kingdom of Bahrain introduced the varicella vaccine as part of the child’s routine immunization schedule in May 2015. Two doses are given to infants at the ages of 12 months and 3 years. This schedule aims to provide children with early protection against varicella infection and its associated complications. Upon introduction, it was expected to reduce the incidence of chickenpox in children. Studies around the effect of the varicella vaccine on the incidence of chickenpox are scarce in GCC countries, including Bahrain [12]. Therefore, this research aims to evaluate the effect of the introduction of the varicella vaccination on the incidence of chickenpox in the Kingdom of Bahrain. The primary objectives of the study were: (1) to estimate vaccine effectiveness (VE) using the screening method, and (2) to investigate changes in incidence and seasonal variation following the introduction of vaccination. The secondary objectives are to compare the infection between different age groups in pediatrics and among adults, healthcare utilization, and hospitalization based on vaccination status, and to identify the predictors of vaccine uptake among cases with chickenpox.
Methods
1. Study design and study setting
A retrospective observational study was conducted on routinely collected surveillance data for all cases diagnosed with chickenpox (varicella) and reported to Public Health Directorate in the Kingdom of Bahrain from 2010 to 2024. In Bahrain, as chickenpox is a notifiable disease, the Public Health law mandates reporting all its cases to the Public Health Directorate of the Ministry of Health.
In 2015, the nationwide varicella vaccination in Bahrain was implemented without a catch-up vaccination program for older children. However, vaccination was also recommended for high-risk groups. Varicella vaccine was recommended for certain risk categories, such as nonimmune healthcare workers in direct contact with patients, healthy susceptible individuals who are close household contact of immunocompromised patients (e.g., siblings of a child with leukemia, or children whose parents are on chemotherapy), and other categories determined by healthcare providers. Vaccination of infants younger than 12 months may be considered in specific circumstances, such as outbreak control or other high-risk situations, according to public health recommendations. Children between 12 months and 3 years of age should receive their first dose before reaching 3 years of age to minimize missed vaccinations (defaulters) and ensure timely completion of the vaccination schedule. The minimum interval between the first and second doses is 12 weeks for children aged 12 months to <13 years and 4 weeks for children aged ≥13 years.
2. Study population
The study included all cases diagnosed with chickenpox and reported to the Public Health Directorate in the Kingdom of Bahrain from 2010 to 2024, including all age groups, both sexes, and all nationalities (Bahraini and non-Bahraini). Data from 2010 to 2013 were limited to aggregate or incomplete records and did not include the demographic, vaccination, and healthcare variables required for the present analysis. Complete individual-level surveillance data were only available from 2014 onward. Accordingly, the 2010–2013 data were used solely to describe annual trends, whereas the 2014–2024 data were used for the epidemiological analysis. Supplementary Fig. 1 outlines the patient selection process. Chickenpox cases are diagnosed based on the clinical picture, symptoms, and type of rashes [9]. Although laboratory confirmation is not required for the diagnosis of varicella, cases with detection of VZV by polymerase chain reaction or viral isolation from vesicular fluid, tissue specimens, or cerebrospinal fluid were included as laboratory-confirmed cases when available [9].
3. Data collection
Data were retrieved from the surveillance database in the Public Health Directorate from 2010 to 2024 and from patient electronic health records. Data collected from the electronic health records included diagnosis date, age, sex, nationality, vaccination status, and date of each vaccine dose (if vaccinated), admission details (if admitted), including date of admission, duration of admission, and discharge date. The data were obtained from electronic health records based on International Classification of Disease (ICD)-10 codes for chickenpox (varicella)-B01, B01.8, and B01.9. Age at diagnosis was based on the age on the reporting date. The age was analyzed as a continuous variable and categorized into predefined age groups. The primary exposure variable of interest was the vaccination status of cases. The cases were categorized into vaccinated (had received one or 2 doses) or unvaccinated. Cases occurring after vaccination were considered as breakthrough varicella infection.
4. Statistical analysis
Data were collected on Microsoft Excel and was coded and analyzed using Stata 18 (StataCorp LLC, College Station, TX, USA). The annual chickenpox incidence rate per 100,000 was calculated annually for the study period using the total population published. The incidence was also analyzed by age group over the study period to explore any shift in the trends. The incidence of chickenpox was compared between vaccinated and nonvaccinated individuals by age group. VE was calculated for the study period.
Descriptive statistics for demographic characteristics of cases by vaccination status were analyzed. Continuous variables were reported as means and standard deviations and compared using independent t test. Categorical variables were described using counts and percentages and were compared using the chi-square test. We use the screening method to estimate the VE in Bahrain [20]. In the screening method, we estimate the VE by comparing the proportion of vaccinated people among cases (PCV) to the vaccination coverage in the total population (PPV).
Based on available published data from Bahrain from 2016 to 2022 [21], the available varicella vaccine coverage was stratified into 2 vaccine-eligible age groups: children aged 1–2 years who had received the first dose of the varicella vaccine and children aged 3 years or older who had received the second dose. Accordingly, VE was calculated only for these 2 age groups. Multivariable binary logistic regression was performed to identify independent factors associated with varicella vaccine uptake, treated as a binary outcome. Adjusted odds ratios (ORs) with 95% confidence intervals were reported, and statistical significance was set at P<0.05.
Results
1. Incidence of chickenpox
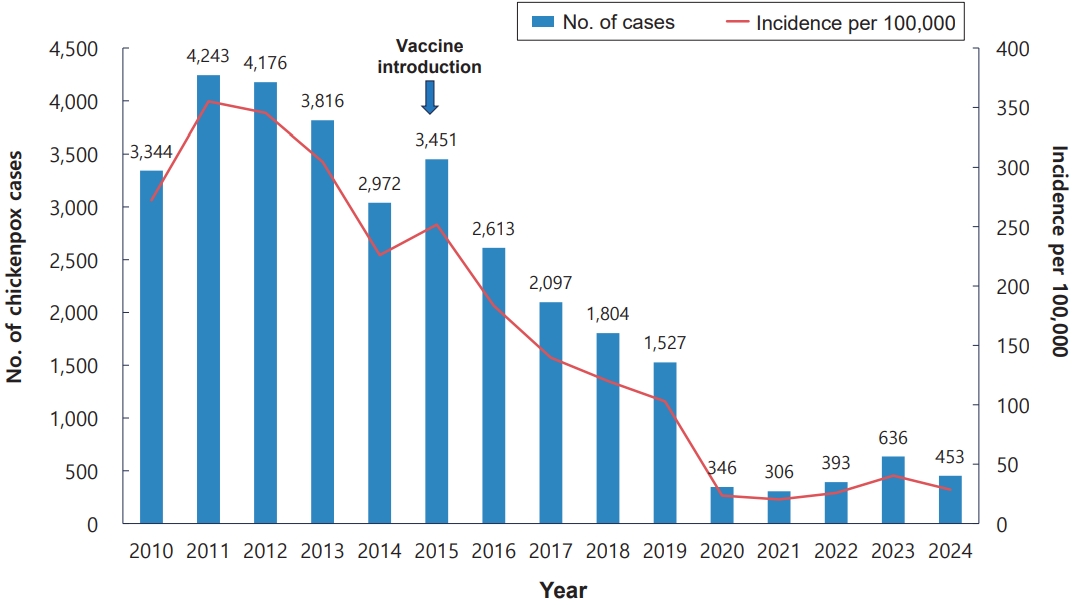
During the study period from 2010 to 2024, a total of 34,499 records were retrieved from the varicella surveillance database. Of these, 32,177 were confirmed chickenpox cases (15,579 cases from the 2010–2013 aggregate annual data and 16,598 cases from the 2014–2024 individual-level data). The number of cases in 2014 before introducing the varicella vaccine was around 2,972 cases. Within 4 years after introducing the vaccine, the number of cases reduced by 55.8%, reaching 1,527 cases in 2019. A further reduction to 453 cases in 2024 was noted (85.9%) (Fig. 1). The incidence of chickenpox was 251.8 per 100,000 of population in 2015 and it reached 28.5 per 100,000 in 2024.
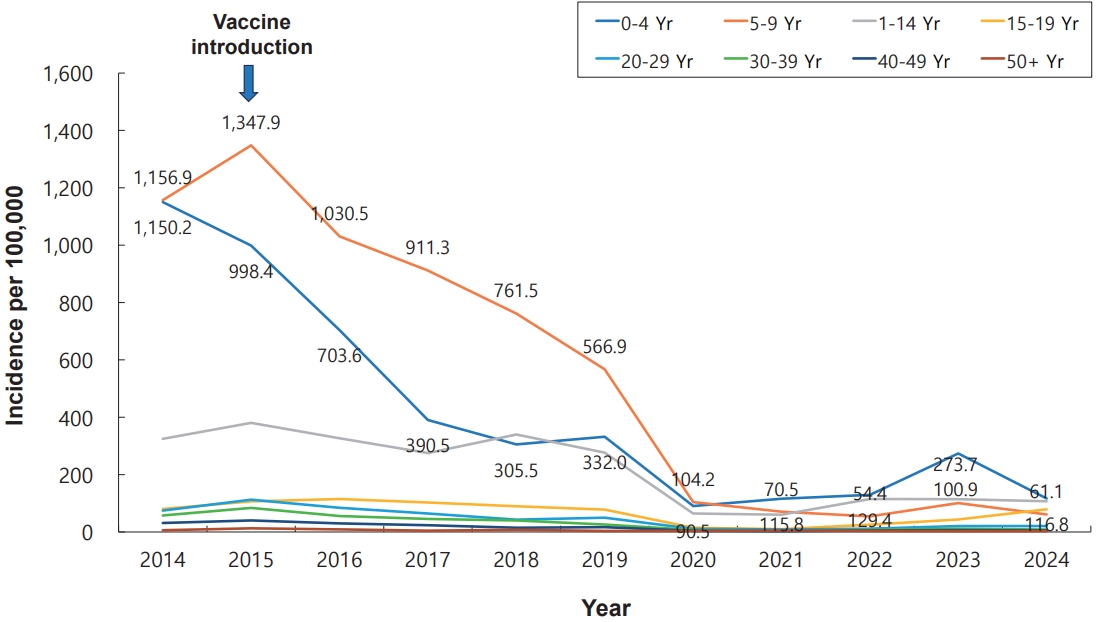
The incidence of chickenpox was higher among children than adults (Fig. 2). In 2014, at the beginning of the study and before the introduction of the chickenpox vaccine in the childhood routine immunization schedule, the highest incidence of chickenpox was among children 0–4 years and 5–9 years, with an incidence of 1,150.2 and 1,156.9 per 100,000, respectively. After the introduction of the vaccine in May 2015, the incidence in both age groups fell sharply reaching 116.8 and 61.1 per 100,000 in 2024, respectively.
2. Seasonality of chickenpox
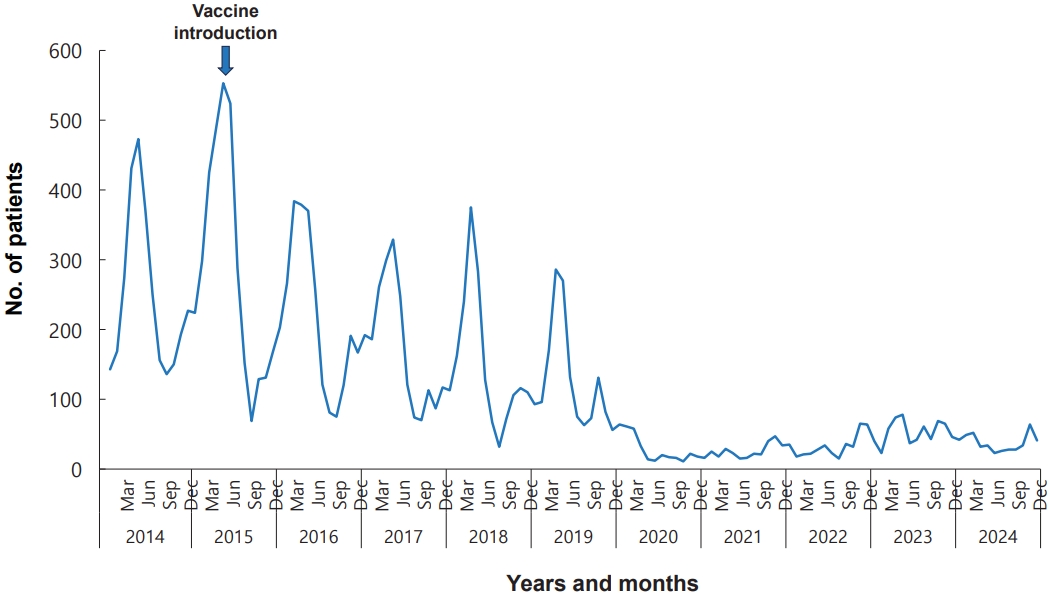
The number of chickenpox cases varied by month, with the highest number reported in April each year (Fig. 3). This seasonality was clear between 2014 and 2019 but became less obvious thereafter when the number of reported cases decreased after introducing the varicella vaccine.
3. Patient characteristics
Table 1 showed the demographic characteristics of cases infected with chickenpox by vaccination status. Most cases were male (n=9,523, 57.4%) and 11,468 (69.1%) of patients were Bahrainis, and 5,130 (30.9%) were non-Bahrainis. The most common age group was between 5 and 9 years (n=5,988, 36.1%), followed by the age group of 0 to 4 years, which accounted for 4,717 (28.4%) of the patients. Comparison of patients by different age groups is shown in Supplementary Table 1. Most children were Bahraini males across all the age groups while most adults were non-Bahraini males.
Most cases were unvaccinated (n=14,955, 90.1%). Most of the vaccinated cases received their vaccine before the age of 4. The vaccine uptake was significantly higher in females, children, Bahraini, and those living in the Northern governorate (P<0.001 each). Cases were mainly seen in primary care (n=16,803, 98.2%). Most cases were mild and only 12 cases (0.1%) were admitted to the hospital; 8 adults and 4 children, and none of them were vaccinated.
4. Vaccine effectiveness
We calculated the proportion of vaccinated people among cases and used the published vaccination coverage for the chickenpox vaccine to calculate the VE each year (Table 2) [21]. From 2016 to 2022, children who received the first dose of vaccination demonstrated a VE ranging from 99% to 100%, whereas older children who received the second dose showed a VE ranging from 97.7% to 100%. Supplementary Fig. 2 illustrates incidence of chickenpox cases and vaccination coverage across different age groups.
5. Predictors of varicella vaccine uptake
A multivariable logistic regression analysis was performed to identify independent demographic and geographic factors associated with varicella vaccine uptake. The model significantly predicted the odds of vaccination (χ²=1962.94, P<0.001; pseudo-R²=0.185). Overall, age group and nationality were significantly associated with vaccination status, whereas sex and governorate were not (Table 3). Age was a strong predictor of vaccination status. Compared with the reference age group (0–4 years), all older age groups had significantly lower odds of vaccination, with the greatest reduction observed among adults aged ≥20 years, who had a 99.7% lower likelihood of being vaccinated (adjusted OR, 0.003; P<0.001). An additional analysis was conducted by separating infants aged <12 months from children aged 1–4 years. The findings were consistent with those of the primary analysis. Because the number of infants was relatively small (196 [1.2%] of the study population), and none had received the vaccine, the original age categorization was retained in the multivariable analysis to preserve statistical power. Non- Bahraini nationals had 25.6% lower odds of vaccination than Bahraini nationals (adjusted OR, 0.744; P<0.001). Sex was not significantly associated with vaccination status (P=0.916). Although the overall effect of governorate was not statistically significant; residents of the Muharraq Governorate had 34.8% higher odds of vaccination than those residing in the reference Capital Governorate (adjusted OR, 1.348; P<0.001), whereas no significant differences were observed for the Northern or Southern Governorates.
Discussion
This study demonstrates a substantial reduction in the annual incidence of reported chickenpox cases following the introduction of varicella vaccine in May 2015. The annual incidence declined from 251.8/105 cases in 2015 prior to the introduction of varicella vaccination program to 28.5/105 in 2024, accounting for an 88.7% reduction. This decline in Bahrain was consistent with regional evidence where the reduction rate ranged from 67.1% to 93.3% [14,22,23]. However, internationally, the reduction rates showed a wider range from 41.7% to 90.4% [15,24]. Supplementary Table 2 summarizes the previously published original studies from countries neighboring Bahrain and worldwide [13-15,22-26]. This substantial reduction in varicella infections reflects the efficacy of this vaccination program.
Analysis of the seasonal pattern of chickenpox incidence in Bahrain showed a clear monthly variation, with consistent peaks in April between 2014 and 2019. This finding is similar to regional data such as those from Saudi Arabia, where chickenpox showed a clear seasonal pattern, with peak activity in March and April [13]. This regional pattern was also reported in Kuwait where seasonal peaks occurred in the April–June period [23]. This pattern may be related to both environmental and social factors. Previous literature suggested that high temperature may reduce varicella virus survival, while overcrowding and close social contact may facilitate transmission [13]. After 2019, the seasonal fluctuation in Bahrain became less clear, with fading of monthly peaks and a more uniform distribution of cases throughout the year. This occurred alongside the marked reduction in overall case numbers, suggesting that the reduction in susceptible individuals after vaccine introduction may have weakened the usual seasonal rise in cases. A similar observation was reported in Italy as well, where varicella hospitalization rates showed spring peaks from February to May; after January 2015, peak incidence rates decreased significantly, and yearly peaks declined further as higher vaccine coverage was achieved [15]. However, this post 2019 pattern should be interpreted with caution, as the marked reduction during 2020–2021 may have been influenced by coronavirus disease 2019 pandemic-related changes in social mixing, the implementation of social distancing, wearing masks, and healthcare seeking behavior, in addition to the effect of vaccination.
Our findings demonstrate a clear and statistically significant age-specific reduction in chickenpox incidence following the introduction of the varicella vaccine into the routine childhood immunization program. The most marked decline was observed among children aged zero to 4 years and 5 to 9 years, with incidence declining sharply following vaccine introduction and continuing to decrease steadily through 2024. These findings are consistent with regional evidence. A longitudinal study from Saudi Arabia reported a 60% reduction in varicella cases among children aged 1–4 years following vaccine introduction, demonstrating the greatest decline among pediatric age groups [14]. A study in Israel demonstrated a decline of 81.4% in incidence among children aged 1–7 years, with the largest estimated reduction observed among 1–2 year olds [22]. Similar age-specific outcomes have been reported in the United States, where population-based surveillance demonstrated 90–95% reductions in incidence among children aged 1–9 years after the implementation of universal varicella vaccination [24]. However, the current study demonstrated a marked reduction in varicella incidence across all age groups following vaccine introduction, with no evidence of a true age shift. Comparable findings have been reported in Saudi Arabia, where the proportion of varicella cases in adults aged ≥40 years increased from 2.2% in the pre-vaccination period to 11.5% after vaccine implementation, despite substantial declines in overall disease incidence [14].
Severe disease was uncommon following the introduction of the varicella vaccine in Bahrain. Among the 16,598 reported cases between 2014 and 2024, more than 98% were managed in primary healthcare settings, and only 12 cases (0.1%) required hospital admission. Notably, none of the hospitalized cases were vaccinated, and most admissions occurred among adults. This pattern suggests that varicella vaccination not only reduced disease incidence but also attenuated disease severity, resulting in minimal need for inpatient care. These findings align with long-term surveillance data from the United States, which demonstrated a 94% reduction in varicella-related hospitalizations and a 97% reduction in deaths following the implementation of universal varicella vaccination [25]. In that context, hospitalization has become a rare event among children, and varicella-related mortality has been practically eliminated in vaccinated cohorts. Furthermore, it was estimated that more than 10,500 hospital admissions are prevented annually as a direct result of vaccination, highlighting the substantial impact of varicella immunization on reducing severe disease and healthcare utilization [25].
The present study demonstrated high VE, ranging from 97.7% to 100%, during the period from 2016 to 2022. In the literature, the effectiveness of a 2–dose varicella vaccination schedule is generally reported to be in the low 90% range [27]. The observed difference may be attributed to several factors, including the use of the screening method, differences in vaccination coverage, surveillance systems, study population, and real-world program implementation.
The multivariable logistic regression findings of this study indicated that chickenpox vaccination uptake was primarily associated with age and nationality, rather than sex or governorate of residence. The substantially lower odds of vaccination among older individuals compared with children aged 0–4 years are in line with the structure of Bahrain’s routine childhood immunization program, which mainly targets young children. This association likely reflects that younger children were more likely to have been reached through scheduled vaccination visits, while older individuals were less likely to have been included at the time of vaccine implementation. The policy of vaccinating children aged 12 months to 3 years, without implementation of a catch-up vaccination program at the time of vaccine introduction may have influenced the observed association between age and vaccine uptake. The lower vaccine uptake among older children is therefore more likely attributable to vaccine eligibility criteria than to age itself.
The lower odds of varicella vaccination observed among non-Bahraini individuals should be interpreted cautiously. This association may be influenced by disparities in healthcare access, lower healthcare utilization for mild disease, differences in case detection, incomplete documentation, variation in reporting patterns, or vaccination received outside the national system, rather than a true reduction in infection risk. Moreover, this finding may partly reflect the demographic profile of the non-Bahraini population, in which many individuals are adult expatriate workers who fall outside the routine pediatric vaccination target group, rather than reflecting lower vaccine acceptance.
The absence of significant associations with sex and governorate suggests that, after adjustment, vaccination uptake was broadly uniform between males and females and did not vary significantly across geographic areas. Taken together, these findings support the effectiveness of Bahrain’s routine childhood immunization program delivery while highlighting the importance of considering demography, eligibility criteria, and documentation limitations when interpreting vaccination uptake among adults and non-Bahraini residents.
This study has several limitations that should be considered when interpreting the findings. First, the analysis relied on routine surveillance and administrative health data, which are inherently subject to underreporting and reporting delays. These factors could have influenced the observed trends in chickenpox incidence, particularly across different phases of vaccine implementation. Second, inaccuracies in population denominators and possible misclassification of vaccination status could have affected the precision of incidence estimates and comparisons between vaccinated and unvaccinated groups. Vaccination records may not fully capture vaccines received outside the public health system or prior to residency in Bahrain. Third, the temporal comparison between the pre- and postvaccination eras may be limited by the relatively short prevaccination period, as data from 2010–2013 were available only as aggregate data and did not include the demographic, vaccination, and healthcare variables required for the analysis. Fourth, although none of the infants with chickenpox below 1 year of age received the varicella vaccine, including them within the same age category as vaccinated or vaccine-eligible children may introduce heterogeneity and could affect the interpretation of the results. Finally, residual confounding cannot be completely excluded. Factors such as socioeconomic status, population mobility, school attendance patterns, and access to healthcare services were not fully accounted for and may have contributed to observed changes in incidence independent of vaccine introduction. Despite these limitations, the use of nationwide mandatory surveillance data provide a comprehensive overview of long-term trends and strengthens the overall validity of the findings.
The persistent and evident drop in chickenpox incidence noticed after the introduction of routine varicella vaccination in Bahrain emphasizes the public health value of maintaining the current immunization policy. The reduction from more than 3,000 reported cases annually before vaccine introduction to fewer than 500 cases in 2024 highlights the vaccine’s role in markedly limiting community transmission and averting recurrent outbreaks. From a healthcare system standpoint, the consistently low number of hospital admissions and predominance of mild cases managed in primary healthcare suggest a reduction in severe disease and healthcare utilization, translating into lower economic burden.
In conclusion, the introduction of varicella vaccine into the routine childhood immunization program in Bahrain was associated with a substantial and sustained reduction in reported chickenpox incidence. The seasonal pattern of chickenpox became less pronounced after the overall reduction in reported cases. The decline was most marked among children, particularly in the age groups targeted by vaccination (0–4 and 5–9 years). Severe disease was rare, most cases were managed in primary healthcare settings, and none of the hospitalized cases were vaccinated. Calculated VE in the period between 2016 and 2022 was between 97.7% and 100%. Patients’ age and nationality were independent predictors for varicella vaccine uptake. These findings support the importance of maintaining high varicella vaccine coverage. Continued surveillance is needed to monitor disease incidence, residual seasonality, age-specific trends, long-term vaccine impact, breakthrough infection, and severe outcomes. Further studies are needed to identify factors that can affect varicella vaccine uptake such as socioeconomic status, population mobility, school attendance patterns, and access to healthcare services.


 PDF Links
 PubReader
 ePub Link
 XML Download
 PubMed
 Download Citation


